

Urology · Jaipur Hospital
Haematuria and Urological Emergencies in Jaipur
Blood in urine or sudden blockage? We assess you fast and give a clear plan.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Treatment length
- Varies by condition
- Anaesthesia
- As required
- Recovery
- Depends on underlying cause
- Price
- ₹5,000 to ₹1,50,000typical range in India; ask us for an estimate
When urine looks wrong
Blood in urine, sudden blockage or injury scares you
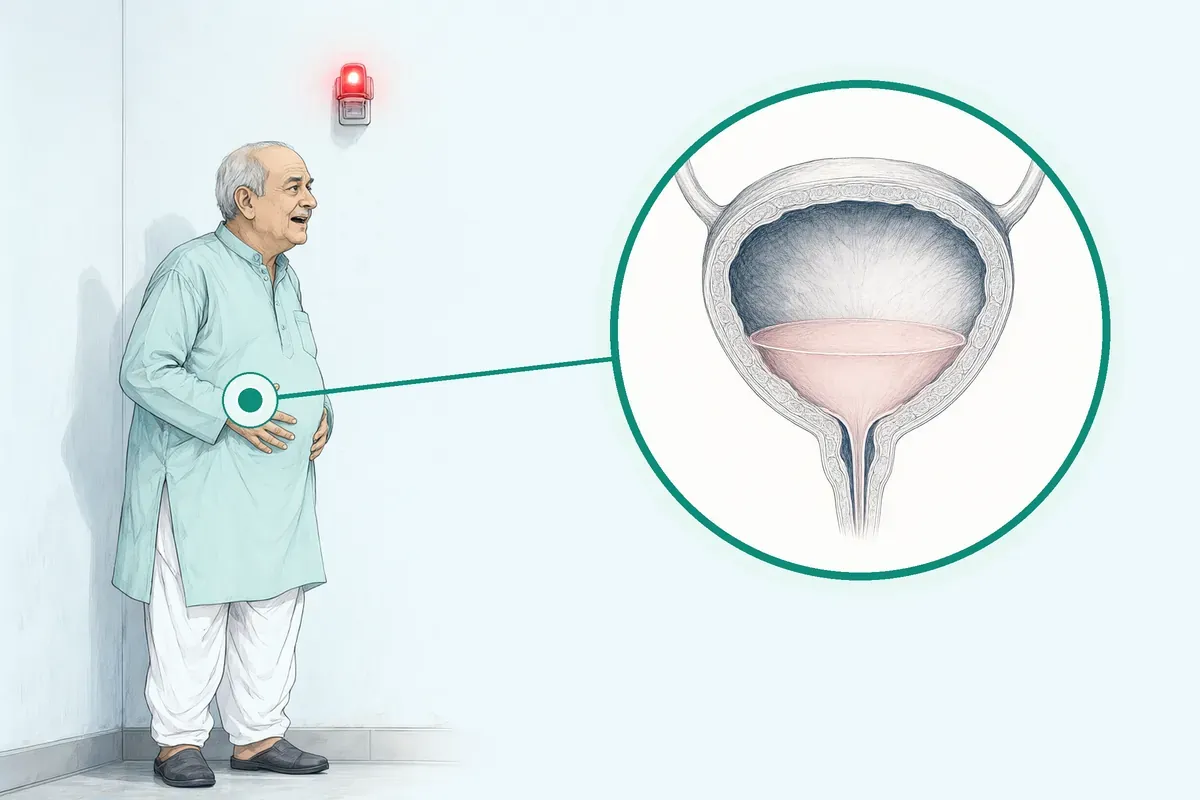
You may see pink or red urine, feel pain, or be unable to pass urine at all. These signs can point to infection, stones, injury or a growth. Waiting can lead to kidney damage or sepsis.
-
Visible blood in urine
Pink, red or cola-coloured urine that you can see.
-
Hidden blood found on test
Urine looks normal but a microscope shows blood cells.
-
Cannot pass urine
Sudden inability to empty the bladder, often with pain.
-
Injury or severe infection
Trauma to the abdomen or groin, or fever with urinary symptoms.
Blood in urine can come from infection, stones, enlarged prostate, kidney disease or cancer.
Why Jaipur Hospital
You worry about what the blood means, whether you will need surgery, and how much time and money it will take.
Your care plan
Your first steps with us
- 1 Call or visit our 24x7 emergency department
- 2 Get examined and urgent tests done in-house
- 3 Review options with your urologist and agree a plan
- 4 Have treatment and attend follow-up visits
How urgent urology problems are managed
Treatment depends on the cause. Your surgeon will discuss the right approach for you.
-
Cystoscopy and clot evacuation
Bladder washout under anaesthesia to clear clots blocking urine flow.
-
Suprapubic catheterisation
A tube placed through the lower abdomen into the bladder when the urethra cannot be used.
-
Emergency nephrostomy
A drain placed through the back into the kidney to relieve obstruction and infection.
-
Angioembolisation
Interventional radiology to block bleeding vessels in the kidney.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
What studies show about urgent urology care
-
97.2% testis survival within 6 hours
Testicular torsion surgery within 6 hours saves the testis in most cases; after 25 to 48 hours survival drops to 24.4%.
-
42% orchiectomy rate in boys
Among boys having surgery for testicular torsion, 42% need the testis removed.
-
Large clots can block urine flow
Blood clots in the bladder can cause acute retention, which is an emergency needing drainage.
If it is left untreated
Delaying care for blood in urine, blockage or trauma can lead to kidney damage, sepsis or loss of the testis.
Life after treatment
Most people return to their usual routine once the cause is treated and the urinary tract is clear.
-
Urine runs clear again
Blood clears and you can pass urine normally.
-
Pain and fever settle
Infection or obstruction is relieved, so discomfort goes away.
-
Regular check-ups if needed
If tests were normal but blood returns, yearly reviews keep kidneys safe.
-
Back to work and family
Recovery time varies, but most people resume daily activities within days to weeks.
Meet the team
Our Urology specialists
Care led by Jaipur Hospital's urology consultants, backed by round-the-clock surgical, diagnostic and critical care support.
Frequently asked questions
Questions patients ask about haematuria and urological emergencies
Which problems are assessed under haematuria and urological emergencies?
In short
Jaipur Hospital assesses blood in the urine, sudden inability to pass urine, injuries to the urinary tract, and severe infections under this service. These conditions need rapid evaluation because they can point to serious underlying causes such as stones, tumours, or blockage.
In detail
The service covers gross and microscopic haematuria, acute urinary retention, trauma to the kidneys, ureters, bladder or urethra, and obstructive pyelonephritis. Evidence shows that large clots can block urine flow and that infections combined with obstruction can become life‑threatening.
Causes include stones, enlarged prostate, cancers, strenuous exercise, sickle cell disease, and glomerular disease. The team uses history, examination, urine tests, imaging and cystoscopy to identify the source quickly.
A common belief
Many people wait hoping the blood will clear on its own, but clots can block the bladder and infection with obstruction can worsen rapidly.
What actually happens
Early assessment prevents complications.
Your next step at Jaipur Hospital
If you notice pink or red urine, cannot pass urine, have flank pain with fever, or have had a recent injury, come to the 24×7 emergency department at Jaipur Hospital. An attendant can help with registration and the in‑house lab and imaging are available round the clock.
How will the doctor decide which tests I need for haematuria or a urological emergency?
In short
The doctor at Jaipur Hospital selects tests based on your history, physical examination findings, and the suspected underlying cause. For haematuria, a microscopic urinalysis confirms blood cells, urine culture checks infection, and blood tests assess kidney function and prostate status. Imaging choices depend on whether the source is likely in the kidneys, bladder, or prostate.
In detail
Evidence shows history guides the diagnostic pathway. If infection is suspected, urine culture and sensitivity are prioritised. For suspected stones or tumours, kidney and bladder ultrasound is the first imaging step; CT urography gives detailed anatomy.
If bladder or urethral bleeding is likely, cystoscopy is indicated. For acute scrotal pain, scrotal ultrasound with Doppler evaluates testicular blood flow and the whirlpool sign of torsion. In obstructive pyelonephritis, ultrasound or CT shows hydronephrosis and guides emergency nephrostomy.
Blood tests include serum creatinine, PSA for men over 50, and complement proteins if glomerular disease is considered. The doctor balances the need for accurate diagnosis with radiation exposure and cost, explaining each test before ordering.
A common belief
Patients often expect a single test, but the workup is tailored.
What actually happens
A dipstick alone is not enough for haematuria; microscopic exam is standard. For testicular pain, Doppler ultrasound is critical to assess blood flow, not just a physical exam. The doctor explains the reasoning for each test.
Your next step at Jaipur Hospital
You will be told which tests are needed and why. Most tests are available in-house at Jaipur Hospital, so they can often be done the same day. Fasting may be required for some blood tests. An attendant can help you move between departments. After results are ready, the doctor reviews them with you and finalises the care plan.
How soon should I expect improvement after the chosen treatment for haematuria and urological emergencies?
In short
Improvement depends on the underlying cause and the treatment given. For clot evacuation or catheterisation, relief is usually immediate. For infections, fever and pain often improve within 24 to 48 hours of antibiotics. Jaipur Hospital monitors recovery closely.
In detail
Evidence shows that after cystoscopy and clot evacuation, urine flow typically resumes at once. Suprapubic catheterisation provides immediate drainage. Emergency nephrostomy relieves obstructive pyelonephritis promptly, with fever settling in one to two days. Angioembolisation stops active bleeding quickly.
For testicular torsion, salvage rates are highest when surgery occurs within six hours; after 24 to 48 hours, salvage drops significantly. Fournier gangrene requires repeated debridements over days.
Recovery from the underlying condition such as stone passage, tumour treatment, or prostate surgery follows its own timeline. Your surgeon will explain the expected course for your specific diagnosis.
A common belief
People often expect all symptoms to vanish at once.
What actually happens
But some conditions need days of antibiotics or further treatment for the root cause like stones or tumours.
Your next step at Jaipur Hospital
You will be reviewed daily while in hospital. After discharge, follow the medication and review schedule given by your urologist. Report any new fever, worsening pain, or fresh bleeding immediately. Most patients need a follow-up visit within one to two weeks.
How does the term "haematuria" relate to haematuria and urological emergencies?
In short
Haematuria is the medical term for blood cells in the urine, and it is the American spelling of haematuria. At Jaipur Hospital, our doctors use the term haematuria in records and discussions, but both spellings mean the same condition that brings patients to the emergency department.
In detail
Evidence defines haematuria as the presence of red blood cells in urine, either visible to the eye (gross haematuria) or seen only under a microscope (microscopic haematuria).
The term covers all causes from infection, stones, and enlarged prostate to cancers of the kidney, bladder, or prostate. Urological emergencies arise when haematuria is accompanied by clot retention, obstructive pyelonephritis, trauma, or testicular torsion.
The spelling difference does not change the clinical approach: urgent evaluation, imaging, and treatment as needed. Our laboratory reports and discharge summaries use the British spelling haematuria, consistent with Indian medical practice.
A common belief
Patients sometimes think the spelling indicates a different disease.
What actually happens
It does not. The urgency and tests are the same regardless of spelling.
Your next step at Jaipur Hospital
If you see the word haematuria on an overseas report or website, understand it is identical to haematuria. Bring any prior reports to your consultation. The team will investigate the cause and advise on treatment.
Does blood in the urine need assessment even if it is or that causes no pain happens only once?
In short
Yes, or that causes no pain single-episode blood in urine still needs assessment. It can be the first sign of bladder or kidney cancer, or other serious conditions. Jaipur Hospital advises urgent evaluation for any haematuria.
In detail
Evidence states that gross haematuria without pain is a classic presentation of urothelial cancers. Microscopic haematuria found incidentally also warrants investigation.
Studies show that even one episode of visible blood should prompt urine microscopy, imaging, and often cystoscopy to rule out malignancy, stones, or glomerular disease. The absence of pain does not reduce the risk.
Guidelines recommend a full workup for any confirmed haematuria in adults, especially over 40 years or with risk factors like smoking. Delaying assessment can allow a treatable cancer to advance. Foods and drugs can discolour urine, but only microscopy confirms true haematuria.
A common belief
Many people ignore it because it stopped and did not hurt.
What actually happens
That delay can miss an early cancer that was curable.
Your next step at Jaipur Hospital
Do not wait for it to happen again. Get a urine microscopy test first. If blood cells are confirmed, you will need imaging (ultrasound or CT) and possibly cystoscopy. The emergency and OPD urology services at Jaipur Hospital can arrange this quickly.
How can I decide whether to seek advice about haematuria evaluation?
In short
Seek advice immediately if you see blood in your urine, even once, or if a routine test shows microscopic haematuria. At Jaipur Hospital, our urology team recommends urgent evaluation for any blood in the urine, especially with pain, fever, or difficulty passing urine.
In detail
Evidence states that anyone of any age can have haematuria. Gross haematuria with symptoms warrants an emergency room visit. Microscopic haematuria found on screening also needs follow-up because it can indicate early kidney disease, stones, or malignancy.
Risk factors such as smoking, age over 50, or family history of urinary cancers lower the threshold for investigation. A urologist will assess symptoms, review medications, and order urinalysis, imaging, or cystoscopy as appropriate.
A common belief
Some people wait to see if it happens again, but a single episode can be the only sign of a serious condition.
What actually happens
Others ignore microscopic blood found on a routine check-up, yet it can be the earliest warning of kidney or bladder cancer.
Your next step at Jaipur Hospital
Do not wait for the bleeding to stop on its own. Contact Jaipur Hospital for a same-day OPD appointment or visit our 24×7 emergency department. An attendant may stay with you. Your surgeon will guide the next steps after initial assessment.
Which urinary symptoms need urgent assessment?
In short
Urgent assessment is needed for visible blood in urine, inability to pass urine, severe flank or lower abdominal pain, fever with urinary symptoms, trauma to the abdomen or perineum, and sudden testicular pain or swelling. At Jaipur Hospital, our 24×7 emergency urology service evaluates these symptoms immediately to prevent complications such as sepsis, kidney damage, or loss of testicular function.
In detail
Evidence identifies several red‑flag symptoms. Gross haematuria with clots can cause acute retention. Acute urinary retention itself leads to bladder overdistension and potential renal impairment. Obstructive pyelonephritis from a stone with fever can progress to sepsis within hours.
Testicular torsion has a four‑ to eight‑hour window for salvage. Fournier gangrene, though rare, spreads rapidly and requires emergency debridement. Our protocol includes rapid triage, bedside ultrasound, blood tests, and immediate access to cystoscopy, suprapubic catheterisation, nephrostomy, or surgical exploration as indicated.
A common belief
People often dismiss burning or frequency as a simple infection, or hope testicular pain will settle.
What actually happens
Delaying care for these red‑flag signs can lead to sepsis, kidney failure, or loss of a testis.
Your next step at Jaipur Hospital
If you experience any of these symptoms, go directly to the emergency department at Jaipur Hospital. We provide 24×7 ambulance service, in‑house laboratory, imaging, and modular operation theatres. An attendant may stay with you. Do not wait for symptoms to worsen — early intervention preserves organ function.
Which symptoms should prompt me to see a specialist?
In short
You should see a specialist at Jaipur Hospital if you notice pink, red, or cola-coloured urine, or if a routine test shows microscopic blood. Other symptoms include difficulty passing urine, a weak stream, frequent urge with little output, flank or lower abdominal pain, testicular pain or swelling, a persistent erection unrelated to sexual activity, or fever with burning urination. Any of these warrant a urology evaluation.
In detail
Gross haematuria is visible blood in urine, while microscopic haematuria is detected only under a microscope; both need investigation per mdanderson.org and kidney.org. Acute urinary retention presents as inability to pass urine with lower abdominal discomfort.
Testicular torsion typically causes severe acute unilateral scrotal pain, nausea, vomiting, and a high-riding testicle with absent cremasteric reflex. Ischaemic priapism is a persistent erection beyond sexual stimulation and is an emergency.
Fournier gangrene shows rapidly spreading redness, swelling, and pain in the genital or perineal area with fever. Obstructive pyelonephritis gives flank pain, fever, and sometimes sepsis.
These symptoms guide the specialist to order urinalysis, urine culture, imaging such as ultrasound or CT, and possibly cystoscopy or blood tests like PSA and creatinine.
A common belief
Some people ignore pink urine thinking it is dehydration or food colour, but evidence shows gross and microscopic haematuria both need investigation.
What actually happens
Testicular pain with nausea is often mistaken for stomach upset, yet it can be torsion needing surgery within hours. A persistent erection is not a sexual issue but a medical emergency.
Your next step at Jaipur Hospital
If you experience any of these symptoms, do not wait for a routine appointment. Attend the 24×7 emergency department at Jaipur Hospital or book an OPD consultation with the urology department. Bring an attendant and any previous reports.
The specialist will take a focused history, examine you, and order the needed tests on the same day. Early assessment helps identify the cause and start appropriate treatment.
How will the results change my care plan for haematuria or a urological emergency?
In short
Test results at Jaipur Hospital directly shape your care plan by confirming the diagnosis, locating the problem, and gauging severity. Normal results with persistent haematuria may lead to scheduled follow-up. Infection results guide antibiotic choice. Stones, tumours, or obstruction determine whether you need observation, medication, endoscopic procedures, or surgery. Emergency findings like torsion or sepsis trigger immediate intervention.
In detail
If urinalysis shows infection, urine culture directs targeted antibiotics. Microscopic haematuria with normal imaging and cystoscopy may only need yearly monitoring per kidney.org. Visible tumours on imaging or cystoscopy lead to biopsy, staging CT, and multidisciplinary cancer planning.
Large obstructing stones may need ureteroscopy or percutaneous nephrolithotomy. Acute retention from clots requires cystoscopic evacuation. Testicular torsion confirmed by absent Doppler flow mandates immediate surgical exploration and orchiopexy or orchiectomy. Ischaemic priapism with confirmed low flow needs cavernosal aspiration and sympathomimetic injection.
Obstructive pyelonephritis with hydronephrosis and sepsis requires emergency nephrostomy. Fournier gangrene with necrotic tissue on examination proceeds to urgent surgical debridement. Each result narrows the options and sets the urgency.
A common belief
Patients sometimes think all haematuria needs surgery, but many cases resolve with antibiotics or observation.
What actually happens
Conversely, normal imaging does not rule out bladder tumours; cystoscopy is still needed. Testicular torsion on ultrasound means immediate theatre, not a wait-and-see approach.
Your next step at Jaipur Hospital
The urologist will discuss results with you and your attendant, explain the diagnosis, and outline the recommended treatment, its typical duration, and expected hospital stay. You will receive a cost estimate within the typical range of ₹5,000 to ₹1,50,000 depending on the procedure. Consent is taken before any intervention.
What should I do if symptoms persist or worsen after treatment for haematuria and urological emergencies?
In short
If symptoms persist or worsen, contact the urology team or return to the emergency department without delay. New fever, increasing pain, fresh bleeding, or inability to pass urine need urgent review. Jaipur Hospital provides 24×7 emergency cover for such situations.
In detail
Evidence indicates that persistent haematuria after initial evaluation may need repeat imaging, cystoscopy, or urine cytology to rule out missed pathology. Worsening flank pain with fever after drainage could mean inadequate drainage or resistant infection needing antibiotic change.
Increasing scrotal pain after detorsion may signal reperfusion injury or compartment syndrome. Large clots reforming after evacuation may need repeat washout. Fournier gangrene can progress rapidly despite initial debridement, requiring further surgery.
The protocol advises that any deterioration is treated as a fresh emergency until proven otherwise. Your attendant should be told to bring you back immediately if you become drowsy, develop low blood pressure, or have uncontrolled pain.
A common belief
Some patients wait for their follow-up appointment hoping things settle.
What actually happens
In urological emergencies, delay can mean kidney damage, sepsis, or loss of the testis.
Your next step at Jaipur Hospital
Keep the discharge summary and medication list handy. Call the hospital on 0141-2551500 or 0141-2554139 if you are unsure. Do not wait for the next scheduled appointment if you feel worse. The emergency department is open all hours.
FAQ library
Questions and answers about haematuria and urological emergencies
When you contact us
Get a clear plan today
Contact Jaipur Hospital for an OPD consultation with a urologist, in-house tests, a plain-word explanation of options, a cost estimate, cashless help and follow-up care.
- A consultation with a urologist in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Haematuria and Urological Emergencies: what to know
What is haematuria and urological emergencies
- Gross haematuria
- Pink, red or dark brown urine you can see
- Microscopic haematuria
- Blood cells seen only under a microscope
Haematuria is the medical name for the presence of blood cells in your urine. You may see pink, red or dark brown urine, which is called gross haematuria. Sometimes the urine looks normal but blood cells are found only under a microscope; this is called microscopic haematuria.
Having blood in your urine does not always mean you have a serious condition. Certain foods like beetroot or some medicines can make urine look red or brown. Dehydration can also make urine darker, and in extreme cases it may appear bloody.
Drinking a lot of water helps wash the blood out of the system but it does not fix the underlying cause.
Urological emergencies are conditions that need urgent evaluation and treatment to prevent lasting damage.
These include:
- Acute urinary retention where you cannot pass urine
- Severe infections that spread to the kidneys or bloodstream
- Trauma to the urinary tract
- Testicular torsion which is a twisting of the spermatic cord that cuts off blood supply to the testis
Testicular torsion is a surgical emergency most commonly seen in adolescence. Priapism is a penile erection that persists beyond or is unrelated to sexual interest or stimulation; the ischaemic type is an emergency. Fournier gangrene is a rare but life-threatening necrotising infection of the external genitalia, perineum and perianal region. Large blood clots blocking urine flow out from the bladder also need immediate care.
Symptoms and warning signs that need urgent care the same day
- Pink, red or brown urine
- Burning or pain while passing urine
- Difficulty starting or weak stream
- Fever with chills
- Nausea or vomiting
- Swelling in scrotum or penis
See a doctor the same day if you notice pink, red or brown urine, especially if you also have:
- Pain in the flank, lower abdomen or groin
- Burning or pain while passing urine
- Difficulty starting or a weak stream
- Fever with chills
- Nausea or vomiting
- Swelling in the scrotum or penis
Sudden severe pain in one testicle, often with nausea and vomiting, is a classic sign of testicular torsion. The affected testis may sit higher than usual and the cremasteric reflex may be absent. In young children, testicular torsion can present as abdominal pain with nausea and vomiting, sometimes mimicking appendicitis.
Go to the emergency department immediately if you cannot pass urine at all, if you pass large blood clots, if you have a persistent painful erection lasting more than four hours, or if you notice rapidly spreading redness, swelling and severe pain in the genital or perineal area with fever. These are time-sensitive emergencies.
In testicular torsion, there is typically a four- to eight-hour window before irreversible ischaemic damage occurs. Delay in treatment may be associated with decreased fertility or may necessitate removal of the testis.
Causes and who is at higher risk
- higher risk Blood-thinning medicines
- higher risk Enlarged prostate
- higher risk Recent urinary tract procedures
- higher risk for prostate-related causes Men over 50
Common causes of blood in urine include:
- Urinary tract infections
- Urinary tract inflammation
- Kidney stones
- Enlarged prostate
- Cancers of the kidney, bladder or prostate
Other causes are:
- Heavy exercise
- Injuries to the urinary tract or muscles
- Recent internal exams such as cystoscopy
- Sickle cell disease
- Polycystic kidney disease
- Glomerular disease which damages the tiny filters in the kidneys
Certain medicines like SGLT2 inhibitors used for diabetes have been associated with Fournier gangrene.
Testicular torsion is usually caused by a bell clapper anomaly where the testis hangs freely inside the scrotum and can twist on the spermatic cord. This anomaly is the primary risk factor and is often present on both sides. Torsion can be complete, partial or intermittent.
It has a bimodal age distribution with a peak in the first year of life and a second surge in adolescence. Priapism can be ischaemic (low flow), arterial (high flow) after blunt perineal trauma, or stuttering (recurrent). Ischaemic priapism is usually idiopathic.
You may be more likely to have haematuria if you have a family history of kidney disease or stones, take blood-thinning medicines, have an enlarged prostate, or have had recent urinary tract procedures. Men over 50 are at higher risk for prostate-related causes. Anyone of any age can have blood in their urine.
How it is diagnosed: examination and tests
- History and examination Symptoms, medicines, abdomen, flanks, genital area
- Urinalysis and urine culture Test strip, microscopic exam, culture for infection
- Blood tests Creatinine, PSA, complement proteins if needed
The doctor will ask about your symptoms, medical history and any medicines you take. A physical examination includes checking the abdomen, flanks and genital area. For acute scrotal pain, a clinical examination of the scrotum is recommended in all boys with right lower quadrant pain.
Testicular torsion is a clinical diagnosis; if history and examination suggest torsion, immediate surgical exploration is indicated and should not be postponed for imaging.
Initial tests usually include a urinalysis with a test strip and a microscopic examination of urine; a dipstick alone is not enough. A urine culture checks for infection.
Blood tests may include:
- Serum creatinine to assess kidney function
- PSA for men over 50
- Complement proteins if glomerular disease is suspected
Imaging typically starts with an ultrasound of the kidneys and bladder to look for:
- Cysts
- Stones
- Tumours
- Other causes
For testicular pain, scrotal ultrasound with colour Doppler is the mainstay; signs like the whirlpool sign, a redundant spermatic cord, altered testicular lie, size discrepancy and echotexture changes help confirm torsion. A CT scan may be done to look for masses in the urinary tract.
Cystoscopy allows direct examination of the bladder and urethra lining and is typically performed if you have gross haematuria. Urine cytology looks for cancer cells. If kidney filter damage is suspected, a kidney biopsy may be needed.
Treatment options without surgery, and when surgery is advised
Treatment depends entirely on the underlying cause. Urinary tract infections are usually treated with antibiotics. An enlarged prostate causing bleeding may be managed with alpha-blockers or 5-alpha-reductase inhibitors like finasteride or dutasteride. If medicines do not control the bleeding, surgery may be suggested. For cancers, care is multidisciplinary and may include surveillance, surgery, radiation, immunotherapy, chemotherapy or hormone therapy.
Sickle cell disease, chronic kidney disease and endometriosis have specific medical treatments. Drinking plenty of fluids helps flush the urinary tract but does not replace specific treatment.
Surgery is advised urgently for several emergencies. In testicular torsion, immediate surgical exploration is needed; if the testis appears salvageable, detorsion and fixation (orchiopexy) is performed, and the opposite testis is also fixed because the bell clapper anomaly is often bilateral. If the testis is completely black and necrotic, it is removed (orchiectomy).
For clot retention where large clots block urine flow, cystoscopy with clot evacuation and bladder washout is done under anaesthesia. If a urethral catheter cannot be passed, suprapubic catheterisation provides urinary diversion. For obstructive pyelonephritis, emergency percutaneous nephrostomy drains the kidney. Severe renal bleeding may need angioembolisation by interventional radiology.
In ischaemic priapism, decompression by aspiration and injection of sympathomimetic drugs is started within four to six hours; if this fails, surgical shunting or early prosthesis implantation may be considered. Arterial priapism is treated by selective embolisation. Fournier gangrene requires extensive surgical debridement, sometimes with faecal diversion.
Preparing for surgery for Haematuria and Urological Emergencies
When you arrive at Jaipur Hospital for an urgent urological problem, the team moves quickly. In the emergency department, a doctor will take a brief history and examine you. Blood tests such as a complete blood count, kidney function, and coagulation profile are usually done to check your fitness for anaesthesia and to guide treatment.
A urine sample is sent for culture and microscopy. Imaging such as an ultrasound of the kidneys and bladder or a CT scan may be performed to locate the source of bleeding, a stone, or an obstruction.
Tell the doctor about every medicine you take, especially blood thinners, aspirin, or drugs for diabetes such as SGLT2 inhibitors. Some of these may need to be held before a procedure.
If surgery or a procedure under anaesthesia is planned, you will be asked to fast for at least six hours. Clear fluids may be allowed up to two hours before; the anaesthetist will confirm this. An attendant should stay with you to help with consent forms and to take you home afterwards.
Bring:
- Your regular medicines
- Any recent test reports
- Your insurance or scheme cards (RGHS, MAA Yojana, CGHS, or private TPA details)
- A change of clothes
The hospital provides an in-house pharmacy and canteen with dietary meals if you need to stay.
How the operation is done for Haematuria and Urological Emergencies
- Cystoscopy and clot evacuation Telescope passed through urethra to wash out clots and inspect bladder
- Suprapubic catheterisation Catheter placed through lower abdomen into bladder when urethral catheter cannot be passed
- Emergency nephrostomy Drainage tube inserted through skin into kidney under imaging guidance
- Angioembolisation Catheter through groin artery to block bleeding vessel with particles or coils
The exact procedure depends on the emergency. Your surgeon will explain which option suits you after reviewing the imaging and your condition. Common techniques used at Jaipur Hospital include:
- Cystoscopy and clot evacuation: A thin telescope is passed through the urethra into the bladder under anaesthesia. Blood clots are washed out and the bladder is inspected for a bleeding point. This is done when clots block urine flow.
- Suprapubic catheterisation: If a urethral catheter cannot be passed — for example, because of a stricture or trauma — a catheter is placed through a small cut in the lower abdomen directly into the bladder. This diverts urine and relieves retention.
- Emergency nephrostomy: For obstructive pyelonephritis or a blocked kidney with infection, a drainage tube is inserted through the skin into the kidney under imaging guidance. This relieves the obstruction and allows infected urine to drain.
- Angioembolisation: For severe renal bleeding that does not stop with conservative measures, an interventional radiologist passes a catheter through the groin artery to the bleeding vessel and blocks it with tiny particles or coils.
On the day of the procedure, you will be taken to a modular operation theatre. The anaesthetist will give either spinal, general, or local anaesthesia with sedation, depending on the procedure and your health. The surgical team uses sterile drapes and monitoring equipment.
After the procedure, you are moved to the recovery area and then to a ward or the intensive care unit if close monitoring is needed. The hospital has a 24×7 intensive care unit and in-house diagnostic laboratory and imaging for any urgent checks.
Risks and possible complications of Haematuria and Urological Emergencies surgery
- Cystoscopy and clot evacuation
- Injury to urethra or bladder, urinary tract infection
- Suprapubic catheterisation
- Bleeding from abdominal wall, rare bowel injury, catheter blockage
- Emergency nephrostomy
- Bleeding from kidney, injury to nearby organs, tube dislodgement
- Angioembolisation
- Groin haematoma, artery damage, reduced kidney function
All procedures carry some risk. The specific risks depend on the technique used and your underlying condition. Common risks include bleeding, infection, and pain at the procedure site. For cystoscopy and clot evacuation, there is a small chance of injury to the urethra or bladder, or a urinary tract infection afterwards.
Suprapubic catheterisation can cause bleeding from the abdominal wall, bowel injury (rare), or catheter blockage. Emergency nephrostomy carries a risk of bleeding from the kidney, injury to nearby organs, or tube dislodgement. Angioembolisation may cause groin haematoma, damage to the artery, or reduced kidney function if blood flow is affected.
In studies of testicular torsion — another urological emergency — delay in treatment is linked to loss of the testis and reduced fertility. When surgery is done within six hours, testicular survival is high; after 24 to 48 hours, survival drops sharply. Atrophy of the testis can occur even after successful detorsion and fixation.
Some studies report antisperm antibodies after torsion, though their effect on fertility is debated. For Fournier gangrene, a rare but life-threatening infection, extensive surgical debridement is needed and complications such as sepsis, acute kidney injury, and limb loss have been reported.
Your surgical team will discuss the risks that apply to your situation. They take steps to reduce complications, such as giving antibiotics when indicated, using careful surgical technique, and monitoring you closely after the procedure.
Recovery and aftercare after Haematuria and Urological Emergencies surgery
Recovery varies with the procedure and the underlying cause. After cystoscopy or catheter placement, you may go home the same day or stay overnight. After nephrostomy or angioembolisation, a stay of two to five days is typical. The hospital stay range in our protocol is observation to three to five days.
In the first days, nurses will monitor your urine output, check the catheter or drainage tube, and give pain relief as needed. You will be encouraged to drink fluids to flush the urinary tract. If you have a catheter, you will be shown how to care for it before discharge. Antibiotics may be prescribed if there was infection.
At home, avoid heavy lifting and strenuous activity for one to two weeks. Keep the catheter or tube site clean and dry.
Watch for:
- Fever
- Increasing pain
- Blood clots in the urine that do not clear with fluids
- The catheter stopping drainage
If any of these occur, call the hospital on 0141-2551500 or 0141-2554139, or return to the 24×7 emergency department. A follow-up appointment is usually scheduled within one to two weeks to review healing, remove any tubes, and discuss further treatment if needed. The in-house pharmacy can dispense your medicines on discharge.
Results of Haematuria and Urological Emergencies surgery
How well the procedure works depends on the condition being treated. For clot retention, cystoscopy and washout usually restores urine flow immediately. For obstructive pyelonephritis, emergency nephrostomy rapidly decompresses the kidney and controls sepsis in most cases. Angioembolisation stops active renal bleeding in a high proportion of patients, though repeat procedures are sometimes needed.
In studies of testicular torsion, early surgery (within six hours) saves the testis in the majority of cases. Long-term endocrine function (testosterone levels) is generally preserved after torsion, whether the testis is saved or removed. However, semen quality can be affected.
Some studies show a significant number of men have reduced sperm count or motility years later, even after successful detorsion. Other studies find no overall difference compared to fertile controls. One study of pregnancy rates in partners of men with prior torsion found no decrease compared to the general population.
For haematuria due to other causes, the outlook depends on the underlying diagnosis. Infections typically clear with antibiotics. Stones may need further procedures. Cancers require multidisciplinary care. Your surgeon will discuss what to expect based on your specific diagnosis.
Cost and insurance for Haematuria and Urological Emergencies in Jaipur
- ₹5,000 to ₹1,50,000 Typical cost range for emergencies
- ₹2,00,000 to ₹3,00,000 Laparoscopic surgeries (planned)
- RGHS, MAA Yojana, CGHS, private insurers and TPAs Empanelled schemes
The typical cost range for evaluation and treatment of urological emergencies at Jaipur Hospital is ₹5,000 to ₹1,50,000. The final amount depends on the condition, the procedure needed, the length of hospital stay, the type of anaesthesia, implants or stents used, medications, and whether intensive care is required.
Diagnostic tests such as CT scans, ultrasound, and laboratory investigations add to the total. Laparoscopic surgeries for related conditions (such as nephrectomy or pyeloplasty) have higher ranges in India, typically ₹2,00,000 to ₹3,00,000, but these are usually planned procedures rather than emergencies.
Jaipur Hospital is empanelled under RGHS, MAA Yojana, and CGHS. We also work with a panel of private insurers and TPAs. If you are covered under any of these schemes, bring your card and any pre-authorisation letter. The admissions team can help verify coverage and explain what is included.
For patients without insurance, a detailed estimate can be provided after the initial assessment. The hospital has an in-house pharmacy and diagnostic laboratory, so most tests and medicines are billed directly.