

Obstetrics and Gynaecology · Jaipur Hospital
Urogynaecology and Pelvic Floor in Jaipur
Leaking urine or feeling a bulge? We assess your pelvic floor and give you a clear plan.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Operation time
- 1 to 2 hours
- Anaesthesia
- Spinal or general anaesthesia
- Recovery
- 4 to 6 weeks for full activity
- Price
- ₹60,000 to ₹1,80,000typical range in India; ask us for an estimate
Leaks, bulge, daily worry
You leak when you laugh or feel something coming down
Stress incontinence and pelvic organ prolapse are common after childbirth, menopause or heavy lifting. They can make you avoid exercise, social events or work.
-
Urine leaks with activity
Coughing, sneezing or lifting causes leakage.
-
Bulge or pressure in vagina
A feeling something is falling out.
-
Frequent or urgent urination
Sudden urge or going often day and night.
-
Bowel problems
Constipation or feeling of incomplete emptying.
Pelvic organ prolapse affects up to 50% of women who have given birth.
Why Jaipur Hospital
You worry about embarrassing leaks, the discomfort of a bulge, and taking weeks off work or home duties.
Your care plan
Your first steps with us
- 1 Call or visit OPD for gynaecology consultation
- 2 Complete urodynamics and imaging in-house
- 3 Review options with your surgeon and get a cost estimate
- 4 Have surgery or start physiotherapy and recover at home
How the operation is done
Surgery is usually done through the vagina or abdomen under spinal or general anaesthesia. It takes one to two hours. You stay two to three nights.
-
Tension-free Vaginal Tape
A mid-urethral sling placed under the urethra to stop stress leaks. Your surgeon will discuss if it suits you.
-
Pelvic Organ Prolapse Repair
Native tissue or mesh-augmented repair done vaginally or abdominally. Your surgeon will discuss the approach.
-
Urodynamic Study
Pressure-flow test to diagnose the type of incontinence. Done in the OPD before any surgery plan.
-
Pelvic Floor Physiotherapy
Biofeedback and Kegel exercises to strengthen muscles. Often tried first or used after surgery.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 3 Obstetrics and Gynaecology consultants
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
What research shows about these treatments
-
62% reduction in incontinence during pregnancy
Pelvic floor physiotherapy reduced urinary incontinence by 62% in pregnant women in clinical studies.
-
10.5% mesh erosion at 7 years
Mesh erosion probability was 10.5% at seven years follow-up in prolapse surgery trials.
-
87% satisfied at 17 years
87.2% of patients reported satisfaction 17 years after prolapse surgery in long-term follow-up.
If it is left untreated
Without treatment, prolapse can worsen, leading to increasing bulge, urinary retention, recurrent infections, kidney strain from obstruction, and worsening bowel symptoms.
Life after treatment
Most women return to normal activity within four to six weeks with better bladder control and no bulge.
-
Control over leaks
Most people cough, laugh or exercise without leaking urine.
-
No vaginal bulge
The feeling of something falling out usually goes away.
-
Return to routine
Most women resume household work and light activity within a few weeks.
-
Better sleep
Fewer night-time bathroom trips mean more rest.



Frequently asked questions
Questions patients ask about urogynaecology and pelvic floor
Which problems are assessed under urogynaecology and pelvic floor?
In short
Urogynaecology and pelvic floor services at Jaipur Hospital assess stress urinary incontinence, urge urinary incontinence, and mixed incontinence. The team also evaluates pelvic organ prolapse including cystocele, rectocele, uterine prolapse, enterocele, and vaginal vault prolapse. Other conditions include overactive bladder, voiding dysfunction, recurrent urinary tract infections, and faecal incontinence related to pelvic floor weakness.
In detail
Evidence shows pelvic organ prolapse may occur in up to 50% of parous women when based on vaginal examination. The main causes include pregnancy and vaginal childbirth, menopause, ageing, repeated heavy lifting, being overweight, chronic constipation with straining, and chronic coughing from smoking or asthma.
Stress incontinence means urine leaks with activity, cough, laugh, or sneeze, while urge incontinence is a sudden uncontrollable urge to urinate. Urodynamic studies help diagnose the incontinence type. The panel identifies first through third line treatments for these conditions.
A common belief
Many people think only leakage is treated, but prolapse, urgency, and bowel symptoms are equally common.
What actually happens
Evidence shows up to 50% of women who have given birth have some prolapse on examination, though only 3 to 6% report symptoms. Causes include childbirth, menopause, heavy lifting, obesity, constipation, and chronic cough.
Your next step at Jaipur Hospital
Your surgeon will take a detailed history and perform a pelvic examination. You may be asked to complete symptom questionnaires. Based on findings, the doctor may order urodynamic studies or imaging. Most assessments are completed in one or two visits.
How will the doctor decide which tests I need?
In short
The doctor at Jaipur Hospital decides tests based on your symptom pattern, examination findings, and the suspected diagnosis. If stress incontinence is the main concern, a cough stress test and urodynamic study may be ordered. For prolapse, the POP-Q staging during examination guides the need for imaging. Overactive bladder symptoms may lead to a bladder diary and urodynamics. Recurrent infections may need urine culture and imaging.
In detail
Urodynamic study is a pressure-flow study that diagnoses the type of incontinence. The panel identifies first through third line treatments based on diagnosis. Guidelines recommend conservative treatment first. Examination includes POP-Q staging for prolapse.
If surgery is considered, urodynamics helps distinguish stress from urge incontinence, which changes the surgical plan. Bladder diaries quantify frequency and urgency. Urine culture rules out infection. Imaging such as ultrasound or MRI may be used for complex prolapse or suspected fistula. The choice is individualised to your presentation.
A common belief
Patients often expect every test at once.
What actually happens
In reality, urodynamics is the key test to distinguish stress from urge incontinence because the surgery differs. Guidelines say treat conservatively first. A bladder diary you keep at home gives real data on frequency and urgency. Imaging is only for complex cases. The doctor avoids unnecessary tests.
Your next step at Jaipur Hospital
Most tests are done as outpatient procedures. Urodynamics takes about 30 to 60 minutes. You may be asked to arrive with a comfortably full bladder. Results are usually available the same day or at the next visit. The surgeon will explain what each test shows and how it changes your options.
How soon should I expect improvement after the chosen treatment for a pelvic floor problem?
In short
At Jaipur Hospital, the timeline for improvement depends on the treatment you receive. Pelvic floor physiotherapy often shows gradual benefit over several weeks. After surgery, most women notice a reduction in leakage or bulge sensation once the initial healing period of four to six weeks is complete.
In detail
Physiotherapy with biofeedback and Kegel exercises typically requires regular sessions over eight to twelve weeks before significant symptom reduction is seen.
Studies report that pelvic floor physiotherapy can reduce urinary incontinence by 62 percent during pregnancy and by 29 percent at three to six months post partum. A pessary can provide immediate mechanical support once correctly fitted.
Surgical procedures such as a tension-free vaginal tape or prolapse repair involve a hospital stay of two to three nights. Full recovery and return to normal activity usually takes four to six weeks, although light activities may resume earlier. Individual response varies based on the severity of the condition, the specific procedure, and overall health.
A common belief
Some expect instant results from surgery, but tissue healing takes time.
What actually happens
Physiotherapy needs consistent practice, not a single session. A pessary works right away but must be fitted correctly.
Your next step at Jaipur Hospital
Your surgeon and physiotherapist will set realistic milestones at your first visit. Follow-up appointments are scheduled to track progress and adjust the plan if needed. If symptoms do not improve as expected, further evaluation is arranged.
How does the term "urogynecology and pelvic floor" relate to urogynaecology and pelvic floor?
In short
The terms "urogynecology and pelvic floor" and "urogynaecology and pelvic floor" refer to the same medical specialty. The difference is only spelling: "urogynecology" is the American English form, while "urogynaecology" is the British and Indian English spelling used at Jaipur Hospital and across India.
In detail
Both terms describe the branch of gynaecology that focuses on pelvic floor disorders in women, including stress urinary incontinence, urge incontinence, overactive bladder, and pelvic organ prolapse such as cystocele, rectocele, uterine prolapse, enterocele, and vaginal vault prolapse.
The specialty combines urology and gynaecology to diagnose and treat these conditions using urodynamic studies, pelvic floor physiotherapy, pessary fitting, medication, and surgery. At Jaipur Hospital, the department offers all these services under one roof, with a team that includes gynaecologists, urologists, and physiotherapists. The spelling "urogynaecology" follows Indian medical convention and is used in our OPD signage, letters, and records.
A common belief
Patients sometimes think they are separate departments.
What actually happens
In India, all NABH-accredited hospitals use the British spelling — urogynaecology.
Your next step at Jaipur Hospital
When searching for care or reading records, you may see either spelling — they mean the same thing. If you have symptoms like leakage with coughing, a vaginal bulge, or frequent urgency, the specialty to consult is urogynaecology and pelvic floor.
How will the type and severity of the pelvic floor problem be assessed?
In short
The type and severity of your pelvic floor problem are assessed through a structured clinical evaluation at Jaipur Hospital. This includes a detailed symptom history, a pelvic examination using the POP-Q staging system, and often urodynamic studies to measure bladder function.
In detail
Your doctor will ask about urinary leakage (stress or urge), frequency, urgency, nocturia, bowel symptoms, and any sensation of a vaginal bulge. The pelvic examination checks for cystocele, rectocele, uterine prolapse, enterocele, or vaginal vault prolapse, and grades each compartment from stage 0 to 4.
Urodynamic studies — pressure-flow tests — help distinguish stress incontinence from overactive bladder and detect voiding dysfunction. A cough stress test may be done during the exam. In some cases, imaging such as ultrasound or MRI is used for complex prolapse.
The assessment also considers your age, menopausal status, obstetric history, previous surgeries, and medical conditions like diabetes or chronic cough. This comprehensive approach ensures the treatment plan matches the exact anatomy and functional problem.
A common belief
A quick look is not enough.
What actually happens
Proper staging and urodynamics prevent wrong surgery — for example, operating for stress leakage when the real problem is overactive bladder.
Your next step at Jaipur Hospital
You will be asked to arrive with a comfortably full bladder for urodynamics. Wear loose clothing for the examination. The assessment usually takes one OPD visit, though urodynamics may be scheduled separately. Bring any previous reports or imaging.
How can I decide whether to seek advice about pelvic organ prolapse repair?
In short
You should consider seeking advice if you feel a vaginal bulge, pressure in the vagina or rectum, urinary leakage with coughing or sneezing, difficulty emptying your bladder or bowel, or if these symptoms interfere with your daily activities. At Jaipur Hospital, the urogynaecology team can assess your symptoms and guide you through the options.
In detail
Pelvic organ prolapse is common — up to 50% of women who have given birth may have some degree on examination, though only 3–6% report bothersome symptoms. Guidelines suggest treatment when symptoms affect your quality of life.
Non-surgical options such as pelvic floor physiotherapy, pessaries, weight loss, managing constipation, and vaginal oestrogen (especially after menopause) are usually tried first. If these do not relieve your symptoms, or if the prolapse is severe, surgical repair may be discussed.
The choice of technique — native tissue repair, mesh-augmented vaginal repair, or abdominal sacrocolpopexy — depends on the compartment involved, previous surgeries, and your overall health.
Your surgeon will explain the typical recovery of four to six weeks and the hospital stay of two to three nights.
A common belief
Many women think a small bulge is normal and must be tolerated.
What actually happens
Guidelines say treatment is based on bother, not just examination findings. You do not have to wait until it is severe.
Your next step at Jaipur Hospital
Start by noting your symptoms and how they affect you. An initial consultation includes a pelvic examination and possibly urodynamic testing. You can then review the treatment plan together.
How could pelvic floor conditions or their treatment affect future pregnancy?
In short
Pelvic floor conditions and their treatments can influence future pregnancy and delivery. At Jaipur Hospital, the surgical team advises that if you plan to have children, surgery for prolapse or incontinence is usually delayed until your family is complete. Pregnancy and vaginal birth can reverse surgical repairs.
In detail
Pregnancy and vaginal childbirth are the main causes of pelvic organ prolapse. If you have surgery before completing your family, the strain of pregnancy and labour may cause the prolapse or incontinence to recur, requiring further treatment.
Guidelines suggest delaying definitive surgical repair until childbearing is finished. In the meantime, symptoms can be managed with pelvic floor physiotherapy, pessaries, and lifestyle modifications.
If you become pregnant after pelvic floor surgery, your obstetrician and urogynaecologist will coordinate care, often recommending caesarean delivery to protect the repair. Mesh repairs carry specific concerns about mesh exposure during pregnancy, though data is limited. The decision balances current symptom burden against future reproductive plans.
A common belief
Some think surgery fixes the problem permanently.
What actually happens
If you get pregnant after repair, the prolapse often comes back. Non-surgical options like pessaries and physio are preferred until you are done having babies.
Your next step at Jaipur Hospital
Discuss your family plans openly at the OPD consultation. The surgeon will outline non-surgical management options for now and the timing for surgery later. If you are already pregnant, pelvic floor physiotherapy is safe and beneficial. To plan your care around future pregnancy, book a consultation at Jaipur Hospital.
Which symptoms should prompt me to see a specialist?
In short
You should see a specialist at Jaipur Hospital if you feel a bulge or pressure in the vagina or rectum, leak urine when you cough, sneeze, laugh, or exercise, have a sudden strong urge to urinate that you cannot control, urinate frequently day or night, feel you cannot empty your bladder fully, suffer from chronic constipation, or notice faecal leakage. These symptoms suggest pelvic floor dysfunction that warrants evaluation.
In detail
Common symptoms of pelvic organ prolapse include pressure in the vagina or rectum, a feeling something is falling out or bulging from the vagina, incontinence, frequent urination, incomplete bladder emptying, and constipation.
Stress incontinence means leakage with activity, cough, laugh, or sneeze, while urge incontinence is a sudden uncontrollable urge. One in three women experiences some form of incontinence. Guidelines recommend physicians specifically ask about urogynecological symptoms and treat conservatively at first. If symptoms interfere with normal activities, treatment may be needed.
A common belief
Many women wait years thinking these are normal after childbirth or with age.
What actually happens
Evidence shows one in three women has incontinence, and prolapse affects up to 50% on examination. Guidelines say doctors should ask about these symptoms specifically and treat conservatively first. If symptoms interfere with daily life, evaluation is recommended.
Your next step at Jaipur Hospital
Keep a symptom diary for a few days noting leakage episodes, urgency, and bowel habits. Bring a list of medicines you take. At the visit, the doctor will examine you and may suggest urodynamic studies. Most patients are seen within a week of referral.
How will the results change my care plan?
In short
Test results at Jaipur Hospital directly shape your care plan. Urodynamics confirming stress incontinence may lead to pelvic floor physiotherapy, a pessary, or a mid-urethral sling. Results showing urge incontinence suggest medications, bladder training, or nerve stimulation. Prolapse stage determines whether observation, pessary, physiotherapy, or surgery is offered. Mixed findings mean a combined approach.
In detail
Evidence shows the tension-free vaginal tape is the current standard surgical treatment for stress incontinence. For prolapse, fascial reconstruction is indicated for primary prolapse, while mesh-based procedures are for recurrences and severe prolapse. Anticholinergics and beta-3 agonists treat overactive bladder.
SNRIs can be prescribed for stress incontinence. Local oestrogen helps stress or urge incontinence and prolapse symptoms. Pessaries alleviate both incontinence and prolapse symptoms. Pelvic floor physiotherapy reduces incontinence by 62% during pregnancy and 29% postpartum. Surgery is considered when conservative options fail and symptoms are severe.
A common belief
Many think one test gives one answer.
What actually happens
But mixed incontinence needs a combined plan. Evidence shows physiotherapy cuts incontinence by 62% in pregnancy and 29% postpartum. Pessaries help both leakage and prolapse. Local oestrogen improves symptoms. Surgery like tension-free tape is standard for stress incontinence, but mesh for prolapse is for severe or recurrent cases. The plan matches your specific results.
Your next step at Jaipur Hospital
After tests, the surgeon will explain the diagnosis and outline options with typical recovery times. You will discuss risks, benefits, and your preferences. A plan is agreed before any procedure is scheduled. Most patients decide within one or two follow-up visits.
What should I do if symptoms persist or worsen after urogynaecology or pelvic floor treatment?
In short
If symptoms persist or worsen after any urogynaecology or pelvic floor treatment, contact your surgical team at Jaipur Hospital without delay. Early review helps identify whether the issue is part of normal healing, a treatable side effect, or a complication needing intervention.
In detail
After surgery, some discomfort, urinary frequency, or mild bleeding can be expected in the first weeks. However, new or increasing pain, heavy bleeding, fever, inability to pass urine, or a recurrent bulge should be reported immediately.
Studies note that de novo overactive bladder symptoms occur in about 12 percent of women after prolapse surgery, and voiding dysfunction in about 9 percent. Mesh erosion, though less common, may present with discharge, pain, or bleeding months later.
For physiotherapy or pessary users, worsening symptoms may mean the device needs refitting or the exercise programme needs adjustment.
Your surgeon will examine you, possibly repeat urodynamics or imaging, and decide on further management, which could include medication, pessary change, or in some cases, revision surgery.
A common belief
Some women wait months thinking it is normal healing.
What actually happens
But early review catches mesh issues, infection, or voiding problems before they become bigger surgeries.
Your next step at Jaipur Hospital
Keep your scheduled follow-up visits at two weeks and six weeks post-operatively. Do not wait for the next appointment if something feels wrong — call the OPD or visit the emergency department. Bring a list of all medications and any pessary you are using.
FAQ library
Questions and answers about urogynaecology and pelvic floor
When you contact us
Get your assessment and plan
Contact Jaipur Hospital for a gynaecology consultation, in-house tests, plain explanations, a cost estimate and cashless insurance help.
- A consultation with a gynaecologist in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Urogynaecology and Pelvic Floor: what to know
What is urogynaecology and pelvic floor conditions
- up to 50 in 100 women who have given birth Prolapse on examination
- 3 to 6 in 100 women Prolapse with symptoms
- About 1 in 3 women Any incontinence
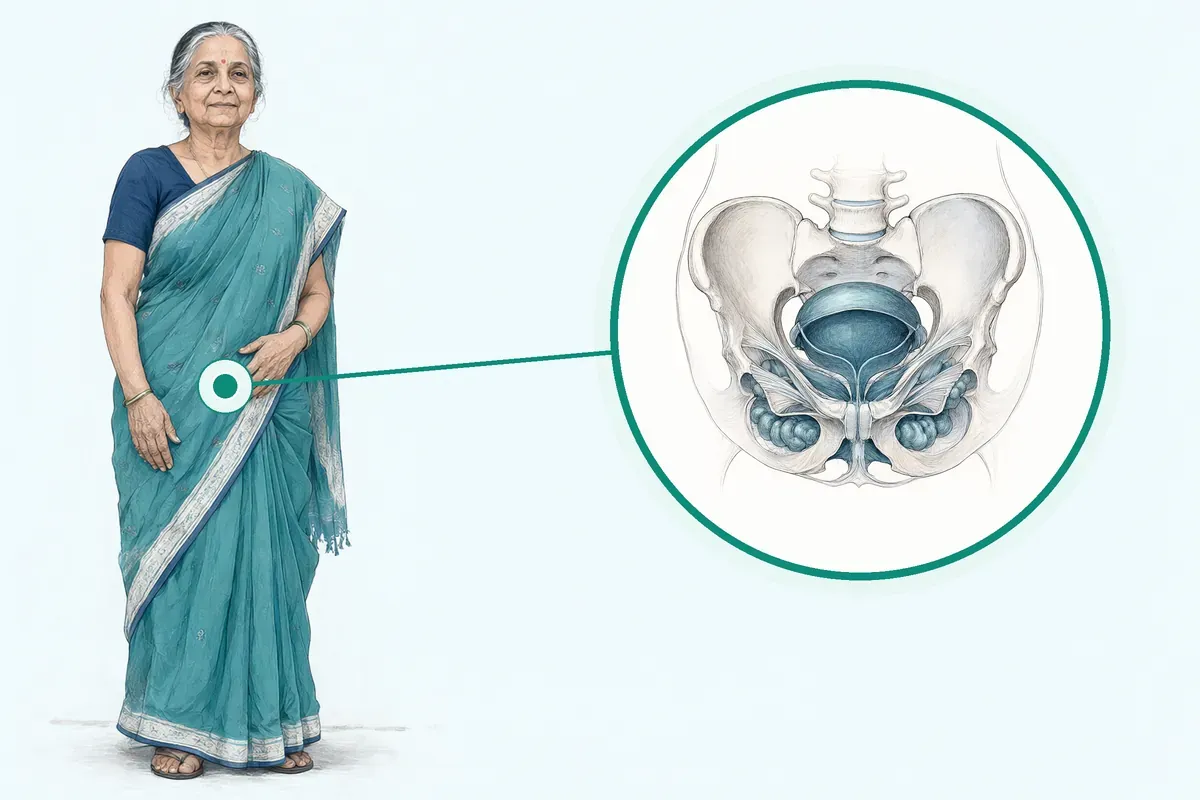
Urogynaecology and pelvic floor care deals with problems that happen when the muscles and tissues supporting the bladder, uterus, vagina and rectum become weak or damaged. The pelvic floor acts like a hammock that holds these organs in place. When it weakens, the organs can drop down and press into the vagina. This is called pelvic organ prolapse.
It may affect:
- The bladder (cystocele)
- The rectum (rectocele)
- The uterus (uterine prolapse)
- The top of the vagina (vaginal vault prolapse)
- The small intestine (enterocele)
Stress urinary incontinence is another common problem. It means you leak urine when you cough, laugh, sneeze or exercise because the support under the urethra is not strong enough. Urge incontinence is a sudden, strong need to pass urine that you cannot control. Some women have both types.
These conditions are common. Studies show that when checked by examination, up to 50 in 100 women who have given birth have some degree of prolapse, though only 3 to 6 in 100 have symptoms they notice. About 1 in 3 women experience some form of incontinence.
Symptoms of pelvic organ prolapse and incontinence and when to seek urgent care
- Cannot pass urine at all
- Severe abdominal pain with vomiting
- Heavy vaginal bleeding not a period
Symptoms can vary. Many women feel a heaviness or pressure in the vagina or rectum. You may feel or see a bulge coming from the vagina, sometimes described as a feeling that something is falling out.
Urinary symptoms are common. You may leak urine with activity, coughing, laughing or sneezing (stress incontinence). You may have a sudden, uncontrollable urge to urinate (urge incontinence). You may need to pass urine often, or feel that your bladder does not empty completely.
Bowel symptoms can include constipation and straining to pass stool.
Most of these symptoms are not emergencies. However, you should seek care the same day if you suddenly cannot pass urine at all, if you have severe abdominal pain with vomiting, if you notice heavy vaginal bleeding that is not a period, or if a prolapsed organ becomes painful, changes colour or you cannot push it back inside. These may mean the organ is trapped or its blood supply is cut off.
Causes and risk factors for pelvic floor problems
- Pregnancy and childbirth
- Stretching and pressure during delivery weaken muscles and tissues.
- Menopause and ageing
- Hormonal changes and ageing reduce tissue strength.
- Raised abdominal pressure
- Overweight, constipation, chronic coughing increase pressure over time.
- Medical conditions
- Diabetes, heart disease, breathing problems, smoking raise surgical risk.
The main cause of pelvic organ prolapse is pregnancy and vaginal childbirth. The stretching and pressure during delivery can weaken the pelvic floor muscles and supporting tissues.
Other causes include the changes of menopause, ageing, and repeated heavy lifting.
Anything that raises pressure inside the abdomen over a long time can contribute. This includes being overweight, being constipated and straining often, and chronic coughing from smoking, asthma or other lung conditions.
If you have surgery for prolapse at a younger age, there is a chance it can come back and need more treatment later. If you are older, your overall health and any past surgeries may affect what type of operation is suitable. Medical conditions such as diabetes, heart disease, breathing problems, or smoking can make surgery riskier.
How urogynaecology and pelvic floor conditions are diagnosed
- Symptom history Doctor asks in detail about urogynecological symptoms.
- Physical examination Pelvic exam checks for prolapse and muscle strength.
- Urodynamic study Pressure-flow test shows how bladder and urethra work.
- Other tests if needed Urine analysis, ultrasound or MRI depending on findings.
Diagnosis starts with your doctor asking about your symptoms in detail. Guidelines say doctors of all relevant specialties should specifically ask about urogynecological symptoms.
A physical examination is done, usually including a pelvic exam to check for prolapse and assess pelvic floor muscle strength. The doctor may ask you to cough or bear down to see if leakage occurs or if a bulge appears.
A urodynamic study is a pressure-flow test that shows how the bladder and urethra work. It helps confirm the type of incontinence and guides treatment planning. This test is available at Jaipur Hospital.
Other tests may include urine analysis to rule out infection, ultrasound, or in some cases MRI. The choice of tests depends on your symptoms and what the examination shows.
Non-surgical treatment options for pelvic floor conditions and when surgery is considered
- Pelvic floor physiotherapy Biofeedback and Kegel exercises
- Vaginal pessary Device to support pelvic organs
- Lifestyle changes Fluids, fibre, weight loss
- Medicines For overactive bladder or stress incontinence
Non-surgical treatments are usually tried first.
Pelvic floor physiotherapy with biofeedback and Kegel exercises strengthens the muscles. In studies, physiotherapy reduced urinary incontinence by 62% during pregnancy and by 29% in the first 3 to 6 months after delivery. Our physiotherapy department provides this care.
A vaginal pessary is a device inserted into the vagina to support the pelvic organs. It is often the first non-surgical option tried. There are many types, and your doctor helps find one that fits comfortably. Pessaries can help with both incontinence and prolapse symptoms.
Lifestyle changes may help. Limiting excessive fluid intake can reduce urinary leakage. Eating more fibre and using stool softeners can ease constipation and straining. If you are overweight, weight loss may improve prolapse symptoms.
For post-menopausal women, vaginal oestrogen may be prescribed to improve vaginal tissue health and reduce symptoms.
Medicines such as anticholinergics or beta-3 agonists are used for overactive bladder with urge incontinence. Selective serotonin-noradrenaline reuptake inhibitors can be prescribed for stress urinary incontinence.
Preventive pelvic floor care during pregnancy and after delivery is recommended.
Surgery is considered if non-surgical options do not work and your symptoms are severe enough to interfere with daily activities. The decision also depends on whether you plan future pregnancies; ideally, surgery is delayed until your family is complete.
Surgical options include tension-free vaginal tape for stress incontinence, and native tissue or mesh-augmented repair for prolapse, done through the vagina or abdomen. Your surgeon will advise which technique suits you.
Preparing for urogynaecology and pelvic floor surgery
Do
- Tell surgeon about all medicines Include blood thinners, diabetes tablets, regular medicines.
- Bring medicines and documents Original packets, allergy list, insurance card, loose clothing.
- Arrange an attendant Someone to stay with you for the first 24 hours at home.
Avoid
- Eat or drink before surgery Fast at least six hours; clear water allowed up to two hours before.
Before surgery your surgeon will ask for a few routine tests.
These usually include:
- Blood counts
- Kidney and liver function
- Blood sugar
- A urine test to rule out infection
A chest X-ray and ECG are common if you are over 45 or have a heart or lung condition. If you take blood thinners, diabetes tablets, or any regular medicine, tell your surgeon at the pre-operative visit. The anaesthetist will decide which medicines to stop and when to restart them.
You will be asked to fast for at least six hours before the operation; clear water may be allowed up to two hours before. Bring your regular medicines in their original packets, a list of allergies, your insurance or scheme card, and comfortable loose clothing for discharge. An attendant should plan to stay with you for the first 24 hours after you go home.
How urogynaecology and pelvic floor surgery is done
The operation is performed under spinal or general anaesthesia and usually takes one to two hours. Your surgeon will discuss which technique suits you. For stress urinary incontinence a tension-free vaginal tape (mid-urethral sling) is a common option.
For pelvic organ prolapse the repair may use your own tissues (native tissue repair) or a mesh-augmented repair done through the vagina or the abdomen. A urodynamic study may be done before surgery to confirm the type of incontinence. On the day of surgery you will be admitted, given the anaesthetic, and a catheter will be placed to drain urine.
The surgical team performs the chosen repair through the vagina or through small abdominal cuts. At the end of the procedure the catheter stays in place and you are moved to the recovery area.
Risks and possible complications of urogynaecology and pelvic floor surgery
- 11.4 percent (64 out of 563) Mesh erosion
- 6.8 percent (32 out of 470) Surgery for mesh erosion
- about 12 percent New bladder overactivity after prolapse surgery
- about 9 percent New voiding difficulty after prolapse surgery
All operations carry some risk.
Common early risks include:
- Bleeding
- Infection
- Pain
- Temporary difficulty passing urine
In studies mesh erosion was reported in 11.4 percent of cases (64 out of 563) and surgical correction for erosion was needed in 6.8 percent (32 out of 470). Blood loss and operating time were significantly higher with transobturator mesh compared with native tissue anterior repair. Recurrences in the apical or posterior compartment were also higher with transobturator mesh.
De novo stress urinary incontinence occurred more often with transobturator mesh than with native tissue repair. After prolapse surgery about 12 percent of women developed new symptoms of bladder overactivity and about 9 percent developed new voiding difficulty. Your surgeon will explain how these numbers apply to your situation and what steps are taken to reduce each risk.
Recovery and aftercare after urogynaecology and pelvic floor surgery
You will stay in hospital for two to three nights. A catheter usually remains for 24 to 48 hours. Pain is managed with regular tablets. You will be encouraged to walk short distances from the first day. Before discharge the team checks that you can pass urine comfortably and that your bowels are moving.
At home, avoid heavy lifting, straining on the toilet, and strenuous exercise for four to six weeks. Light walking and daily activities can increase gradually. Keep the wound area clean and dry. Attend the follow-up appointment usually scheduled at two weeks.
Call the hospital if you develop:
- Fever
- Heavy vaginal bleeding
- Foul-smelling discharge
- Inability to pass urine
- Severe pain not relieved by tablets
- Redness and swelling around any abdominal cuts
Pelvic floor physiotherapy with biofeedback and Kegel exercises is often advised after the initial healing phase to strengthen the muscles.
Results of urogynaecology and pelvic floor surgery in studies
In studies abdominal sacrocolpopexy is considered the most durable prolapse surgery. It was associated with a lower rate of recurrent vault prolapse and less painful intercourse than vaginal sacrospinous colpopexy. Sacral colpopexy also showed a higher success rate on examination and lower reoperation rate than high vaginal uterosacral suspension and a lower reoperation rate than transvaginal polypropylene mesh.
Native tissue anterior repair had more recurrent anterior compartment prolapse than when supplemented with absorbable mesh inlay, but there was no difference in patient awareness of prolapse between the two. Standard anterior repair had more anterior compartment prolapse on examination than polypropylene mesh repair, and awareness of prolapse was higher after standard repair.
The recurrence rate on examination was higher with native tissue repair compared with transvaginal polypropylene mesh. Posterior vaginal repair had fewer recurrent symptoms and lower recurrence on examination than transanal repair. In one long-term study 87.2 percent of patients were satisfied with the outcome 17 years after surgery.
Urethropexy performed at the time of prolapse surgery prevented stress urinary incontinence longer than no urethropexy. Mesh erosion probability at seven years was estimated at 10.5 percent. Your surgeon will discuss what these findings mean for your expected outcome.
Cost and insurance for urogynaecology and pelvic floor surgery in Jaipur
The typical price range for these procedures in India is ₹60,000 to ₹1,80,000. The final amount depends on the type of repair (native tissue or mesh), the surgical route (vaginal, abdominal, laparoscopic), the length of stay, the anaesthesia choice, and any additional tests such as urodynamics. Jaipur Hospital is a NABH-accredited multispeciality hospital established in February 1991.
It accepts:
- RGHS
- MAA Yojana
- CGHS
- A panel of private insurers and TPAs
The hospital has modular operation theatres, a 24×7 emergency department, in-house pharmacy, and in-house diagnostic laboratory and imaging. For an estimate specific to your case, contact the hospital on 0141-2551500, 0141-2554139, or +91-7414-001-001, or email [email protected].