

Pulmonology · Jaipur Hospital
Lung Cancer and Nodule Care in Jaipur
A lung nodule found on a scan. We give you a clear assessment and a step-by-step plan.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Treatment length
- Varies: Diagnostic workup 1 to 2 weeksTreatment cycles 3 to 6 months
- Anaesthesia
- Varies per modality (surgery: GeneralRadiation: None · Chemo: None)
- Recovery
- Surgery: 4 to 6 weeksChemo/Immunotherapy: Ongoing cycles · Radiation: 6 to 8 weeks
- Price
- ₹1,50,000 to ₹15,00,000 (full treatment course)typical range in India; ask us for an estimate
A spot on your lung
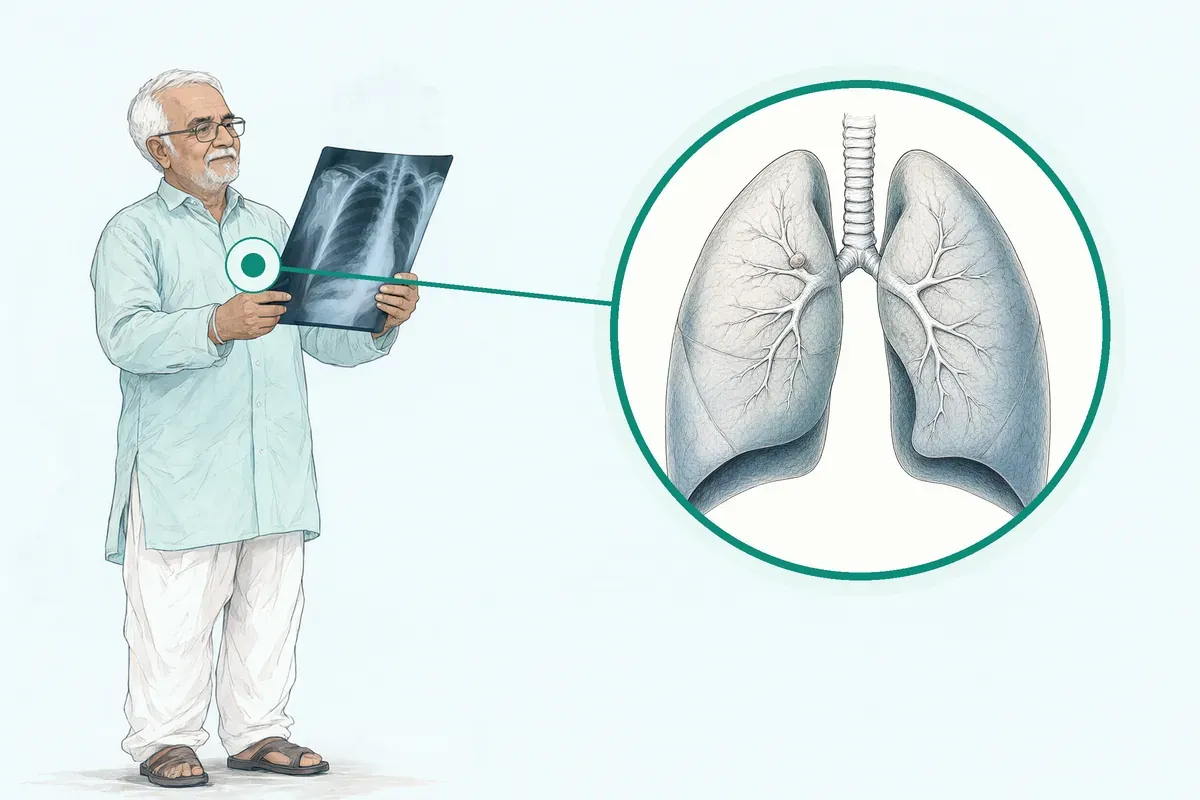
You found a nodule and do not know what it means
Most nodules are not cancer, but waiting without a plan creates worry. You need to know if a biopsy is needed, what the stage is, and what treatment options exist.
-
Unclear scan results
A CT scan shows a nodule but cannot confirm if it is cancer.
-
Biopsy confusion
You are unsure which biopsy method fits your nodule location and health.
-
Treatment overwhelm
Surgery, chemotherapy, radiation, targeted therapy — you need one clear sequence.
-
Cost and logistics
You want a cost estimate and help with cashless schemes before you commit.
Radiologists see pulmonary nodules in nearly 1 out of every 3 chest CT scans.
Why Jaipur Hospital
You worry about what this spot means for your family, your job, and your savings.
Your care plan
Your first steps with us
- 1 Book an OPD consultation with a pulmonologist
- 2 Complete staging scans and biopsy in-house
- 3 Review tumour board plan with your surgeon
- 4 Start treatment and attend scheduled follow-ups
How evaluation and treatment planning work
A multidisciplinary tumour board reviews your imaging, pathology and molecular profile to recommend a personalised sequence of surgery, radiation or systemic therapy.
-
CT-Guided Percutaneous Biopsy
A needle biopsy through the skin for nodules near the lung surface, done under local anaesthesia with CT guidance.
-
EBUS / EUS Guided Staging
A bronchoscope or endoscope with ultrasound samples lymph nodes in the chest to stage the cancer without open surgery.
-
Multidisciplinary Tumour Board
Pulmonologist, oncologist, thoracic surgeon, radiologist and pathologist meet to agree on one coordinated plan for you.
-
Targeted Therapy / Immunotherapy
EGFR, ALK, ROS1 testing guides whether oral targeted drugs or immunotherapy suit your tumour biology.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 1 Pulmonology consultants
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
What studies show about current treatments
-
Median progression-free survival 18.9 months with osimertinib
In EGFR-mutated advanced NSCLC, osimertinib nearly doubled progression-free time versus standard EGFR-TKIs (10.2 months).
-
Grade 3-4 adverse events in 10% with nivolumab
Severe treatment-related side effects were lower with nivolumab (10%) than with docetaxel (54%) in previously treated advanced NSCLC.
-
12-month overall survival 51% with nivolumab
At one year, 51% of patients on nivolumab were alive versus 39% on docetaxel in advanced squamous NSCLC.
If it is left untreated
If a cancerous nodule is not evaluated, it can grow and spread to lymph nodes or other organs, making treatment more complex and reducing options. Most lung nodules are benign, but only biopsy or surveillance confirms this.
Life after your treatment plan starts
Most people return to daily routines between treatment cycles, with regular scans and clinic visits to monitor progress.
-
Clear schedule
You know the dates for chemo, radiation or immunotherapy cycles and when to come for review.
-
Managed side effects
Nausea, fatigue or low counts are addressed early by the nursing and pharmacy team.
-
Regular surveillance
CT scans every few months track response and catch any change early.
-
Attendant support
A family member can stay with you during admission; canteen provides dietary meals.

Frequently asked questions
Questions patients ask about lung cancer and nodule care
Which problems are assessed under lung cancer and nodule care?
In short
Lung cancer and nodule care at Jaipur Hospital covers the evaluation of pulmonary nodules found on imaging and the staging and treatment planning of confirmed lung cancer. The service includes multidisciplinary review by pulmonologists, oncologists, thoracic surgeons, radiologists and pathologists.
In detail
Pulmonary nodules are areas of abnormal growth seen on chest X-rays or CT scans. Most are benign, caused by infections, inflammation, scarring or inhaled particles, but some represent early cancer.
The team assesses nodule size, shape and density — solid, ground-glass or part-solid — and your risk factors such as smoking history.
For suspicious nodules larger than 9 millimetres or those with concerning features, the tumour board guides the next step, which may be CT-guided percutaneous biopsy for peripheral nodules or EBUS and EUS for mediastinal nodal staging.
Molecular testing such as EGFR, ALK and ROS1 is arranged when cancer is confirmed to guide targeted therapy or immunotherapy decisions.
A common belief
Many people assume a nodule means cancer, but most are benign — caused by old infections, inflammation or scarring.
What actually happens
The team looks at size, shape and your risk factors before deciding on biopsy or surveillance.
Your next step at Jaipur Hospital
If a nodule has been found on a scan, bring the images and reports to the OPD. The team will review them and usually complete the diagnostic workup within one to two weeks. You can book a consultation at Jaipur Hospital to start the multidisciplinary evaluation.
How will the doctor decide which tests I need?
In short
The doctor at Jaipur Hospital decides tests based on nodule size, appearance on CT, your risk factors, and overall health. Small smooth nodules under 6 millimetres often need only surveillance. Larger or suspicious nodules typically need PET-CT and biopsy via CT-guided, EBUS, or surgical methods.
In detail
Guidelines suggest nodules smaller than 6 millimetres with smooth edges are usually less likely cancerous. A biopsy is likely recommended if a nodule exceeds 9 millimetres or you have risk factors. The doctor considers whether the nodule is solid, ground-glass, or part-solid.
PET-CT helps assess metabolic activity and distant spread. For tissue diagnosis, options include CT-guided percutaneous biopsy for peripheral nodules, EBUS or EUS for mediastinal nodes, or surgical biopsy.
Molecular testing for EGFR, ALK, ROS1, and PD-L1 is standard for advanced non-small cell lung cancer to guide targeted therapy or immunotherapy. The tumour board reviews complex cases.
A common belief
Some patients think every nodule needs an immediate biopsy.
What actually happens
But biopsy carries risks like pneumothorax. For very small nodules, the risk of biopsy outweighs the benefit. The team follows evidence-based criteria to avoid unnecessary procedures.
Your next step at Jaipur Hospital
After the consultation, the team schedules the appropriate tests. PET-CT and blood work are often done within days. Biopsy may need a short admission or daycare slot. Molecular results take one to two weeks. The tumour board meets weekly.
How soon should I expect improvement after the chosen lung cancer treatment?
In short
Improvement timelines depend on the treatment type. At Jaipur Hospital, surgery recovery takes four to six weeks, radiation effects appear over six to eight weeks, and chemotherapy or immunotherapy cycles continue over three to six months. Your oncologist will set realistic expectations based on your specific plan.
In detail
Evidence from clinical studies shows varied response patterns. For immunotherapy such as nivolumab or pembrolizumab, overall survival benefit emerges over months; median overall survival was 12.2 months with nivolumab versus 9.4 months with docetaxel in one study.
Targeted therapy with osimertinib showed median progression-free survival of 18.9 months. Chemotherapy responses are typically assessed after two to three cycles. Radiation-related symptom relief such as reduced cough or breathlessness often begins during or shortly after the six to eight week course.
Each modality has its own trajectory, and the tumour board tailors the plan to your cancer stage, mutation profile, and overall health.
A common belief
Patients often expect immediate relief.
What actually happens
In studies, immunotherapy survival benefits appear over months, not days. Targeted drugs like osimertinib show progression-free survival near 19 months, but tumour shrinkage takes weeks. Chemotherapy response is usually checked after two to three cycles. Patience and regular follow-up are essential.
Your next step at Jaipur Hospital
Your treating team will schedule regular imaging and clinic visits to monitor response. Follow-up scans are usually done every six to twelve weeks during active treatment. Report any new or worsening symptoms promptly.
What do the type, grade, and stage mean for lung cancer?
In short
Type, grade, and stage describe the cancer's behaviour and spread. At Jaipur Hospital, the tumour board uses these to plan treatment. Type refers to small cell or non-small cell and molecular subtype. Grade reflects how abnormal cells look. Stage describes tumour size and spread to nodes or distant organs.
In detail
Evidence shows non-small cell lung cancer includes adenocarcinoma, squamous cell, and large cell types. Molecular testing for EGFR, ALK, ROS1 mutations guides targeted therapy. Small cell lung cancer is staged as limited or extensive. Grade ranges from well-differentiated to poorly differentiated.
Stage uses the TNM system: T for tumour size and invasion, N for lymph node involvement, M for distant metastasis. Stages I to III are potentially curable with surgery, radiation, or combined modality. Stage IV indicates metastatic disease treated with systemic therapy.
Next-generation sequencing identifies mutations that determine eligibility for oral targeted drugs or immunotherapy. The multidisciplinary team correlates pathology, imaging, and molecular results to assign accurate stage and select therapy.
A common belief
Patients often confuse grade with stage.
What actually happens
Grade is a microscopic feature; stage is about spread. Molecular type — like EGFR or ALK mutation — matters more than grade for choosing targeted therapy. Stage IV does not mean untreatable; it means systemic therapy is the main approach. The tumour board at Jaipur Hospital integrates pathology, imaging, and genomics for precise staging.
Your next step at Jaipur Hospital
Your oncologist will explain your specific type, grade, and stage after all tests are complete. Molecular results may take one to two weeks. Treatment planning follows the tumour board discussion.
How can I decide whether to seek advice about lung nodule evaluation?
In short
You should seek advice about lung nodule evaluation if a nodule was found on a chest X-ray or CT scan, especially if it is larger than 6 mm, has irregular edges, or if you have risk factors such as smoking history, family history of lung cancer, or past cancer. Jaipur Hospital offers a structured assessment to determine the next step.
In detail
Most pulmonary nodules are benign. Radiologists see nodules in nearly one in three chest CT scans. Features that raise concern include size above 9 mm, spiculated or irregular margins, part-solid or ground-glass appearance, and growth on serial imaging.
Risk factors include age over 50, current or former smoking, occupational exposure to asbestos or silica, and prior malignancy. Guidelines suggest that nodules under 6 mm with low-risk features usually need no immediate action; a follow-up CT at twelve months is typical.
Nodules 6 to 8 mm may need a three- to six-month follow-up. Nodules over 8 mm or those with suspicious features often warrant PET-CT or biopsy. EBUS or CT-guided percutaneous biopsy provides tissue diagnosis.
The multidisciplinary tumour board at Jaipur Hospital reviews imaging and risk factors to recommend observation, further imaging, or biopsy. Early evaluation avoids unnecessary procedures for benign nodules while catching cancer when it is most treatable.
A common belief
Many people panic when they hear 'spot on the lung'.
What actually happens
In fact, nodules appear in one in three chest CTs and most are harmless. The mistake is ignoring a nodule that has high-risk features or skipping follow-up scans that detect growth early.
Your next step at Jaipur Hospital
If you have a report mentioning a lung nodule, bring it to the pulmonology OPD. The doctor will review the images, ask about smoking and exposure history, and decide on a surveillance schedule or further tests.
A CT-guided biopsy or EBUS can be arranged within the diagnostic workup window of one to two weeks. Observation follow-ups are typically at six to twelve months.
Which changes in breathing, chest symptoms, or oxygen levels need urgent help?
In short
Seek urgent help at Jaipur Hospital if you develop sudden shortness of breath, new or worsening chest pain, coughing up blood, fever with breathlessness, confusion, or a drop in oxygen saturation below 94 percent on a pulse oximeter. These may indicate infection, tumour progression, pulmonary embolism or treatment complication.
In detail
Small lung nodules rarely cause symptoms. However, lung cancer and its treatment can lead to serious complications. Tumour growth may obstruct an airway, causing breathlessness or collapse of lung tissue.
Cancer increases the risk of blood clots in the lungs, presenting as sudden breathlessness and chest pain. Chemotherapy and immunotherapy can cause lung inflammation (pneumonitis), with fever, cough and falling oxygen levels.
Evidence shows grade 3 or 4 treatment-related adverse events occurred in 10 percent of patients on nivolumab and 54 percent on docetaxel. Radiation can cause oesophagitis or pneumonitis weeks after completion. Pleural effusion from cancer or infection causes progressive breathlessness.
Any rapid change in breathing, new chest pain, haemoptysis, or oxygen saturation below 94 percent warrants immediate evaluation in the 24-hour emergency department.
A common belief
Patients often wait to see if breathlessness passes.
What actually happens
But in lung cancer, sudden changes can mean a clot, infection or treatment reaction. Delaying can be dangerous. A pulse oximeter at home helps you decide faster.
Your next step at Jaipur Hospital
Keep a pulse oximeter at home during treatment. If oxygen drops below 94 percent, or you have sudden breathlessness, chest pain or cough up blood, go to the emergency department immediately. Jaipur Hospital has 24-hour emergency, ambulance, ICU and in-house lab services.
Which symptoms should prompt me to see a specialist?
In short
See a specialist if you have a persistent cough, coughing up blood, unexplained weight loss, breathlessness, chest pain, hoarseness, or recurrent chest infections. These symptoms may indicate a lung nodule or cancer that needs evaluation.
In detail
Small lung nodules rarely cause symptoms. When a growth presses on the airway or is cancerous, symptoms such as cough, haemoptysis, weight loss, breathlessness, chest pain, hoarseness, or recurrent infections can appear.
Risk factors like smoking history, occupational exposure, or family history increase the likelihood that a nodule is malignant.
The team uses these clinical clues along with imaging features — size over 9 millimetres, irregular edges, or growth on serial scans — to decide on biopsy or surveillance.
A common belief
People often wait because small nodules are usually silent.
What actually happens
Symptoms appear only when a nodule grows large enough to press on structures or becomes cancerous. Early evaluation catches treatable disease before it spreads.
Your next step at Jaipur Hospital
Note when each symptom started and whether it is changing. Carry any previous X-rays or CT scans. The doctor will examine you, review imaging, and may order blood tests, PET-CT, or biopsy.
How will the results change my care plan for lung cancer and nodule care?
In short
Results from imaging, biopsy and molecular testing directly shape your care plan at Jaipur Hospital. Benign results may lead to surveillance only. A cancer diagnosis triggers staging, and molecular results such as EGFR, ALK or ROS1 mutations determine whether targeted therapy, immunotherapy or chemotherapy is offered first.
In detail
If the nodule is benign or very low risk, the tumour board recommends a schedule of follow-up CT scans — typically at six to twelve months — and stops if the nodule is stable for two years.
If cancer is confirmed, the stage (early, locally advanced or metastatic) decides the modality: surgery for early stage, combined chemoradiation for locally advanced, and systemic therapy for stage four.
Molecular profiling is critical: EGFR mutations qualify you for oral osimertinib; ALK or ROS1 rearrangements for specific inhibitors; high PD-L1 expression may favour pembrolizumab immunotherapy. The multidisciplinary board reviews every result together to sequence treatments correctly and avoid ineffective chemotherapy when a targeted option exists. Waiting for molecular results before starting systemic therapy is standard practice.
A common belief
A common mistake is starting chemotherapy before molecular results return.
What actually happens
Studies show targeted drugs like osimertinib give longer progression-free survival than chemotherapy for EGFR-mutated tumours. The tumour board waits for the full profile to pick the most effective first treatment.
Your next step at Jaipur Hospital
The full workup and tumour board discussion usually take one to two weeks. Once the plan is finalised, the team explains the sequence, expected duration and costs.
What should I do if symptoms persist or worsen during lung cancer treatment?
In short
Contact your treating team at Jaipur Hospital immediately if you develop new breathlessness, persistent fever, uncontrolled pain, coughing blood, or sudden swelling in the legs. These may signal infection, progression, or treatment side effects needing urgent assessment. Do not wait for the next scheduled visit.
In detail
Evidence shows treatment-related adverse events of grade 3 or 4 occurred in 10 percent of patients receiving nivolumab and 54 percent receiving docetaxel. Immunotherapy can cause immune-related inflammation in the lungs, liver, or endocrine glands. Chemotherapy often lowers blood counts, raising infection risk.
Radiation may cause oesophagitis or pneumonitis weeks after completion. The multidisciplinary team monitors for these complications. Early reporting allows dose adjustment, supportive medication, or hospital admission if required. Your oncologist and pulmonologist coordinate care through the tumour board.
A common belief
Some patients try to manage side effects at home, hoping they will pass.
What actually happens
Studies show serious adverse events occur in up to 54 percent of chemotherapy patients and 10 percent on immunotherapy. Early reporting lets the team adjust treatment, give supportive drugs, or admit you if needed. The 24×7 emergency department at Jaipur Hospital is equipped for urgent oncology complications.
Your next step at Jaipur Hospital
Keep the 24-hour emergency numbers accessible: 0141-2551500 and +91-7414-001-001. The hospital has a 24×7 emergency department, ICU, and in-house pharmacy. An attendant should accompany you for any urgent visit.
Has the lung cancer spread, and which tests can assess that?
In short
Whether cancer has spread is determined by staging tests. At Jaipur Hospital, the standard workup includes contrast-enhanced CT chest and abdomen, PET-CT, brain MRI, and EBUS or EUS-guided mediastinal nodal staging. The tumour board reviews all imaging to assign accurate stage.
In detail
Evidence supports a stepwise approach. CT chest and upper abdomen evaluate the primary tumour, lymph nodes, liver, and adrenal glands. PET-CT detects metabolically active disease elsewhere. Brain MRI is recommended because lung cancer frequently metastasises to the brain.
EBUS or EUS-guided staging provides minimally invasive mediastinal nodal sampling with high accuracy. For peripheral nodules, CT-guided percutaneous biopsy obtains tissue. Molecular testing on biopsy tissue includes EGFR, ALK, ROS1, and broader next-generation sequencing panels.
The multidisciplinary tumour board — pulmonologist, oncologist, thoracic surgeon, radiologist, pathologist — correlates all results to confirm stage and guide treatment. Staging directly determines whether surgery, radiation, or systemic therapy is appropriate.
A common belief
Some patients think a chest X-ray is enough.
What actually happens
It is not. Lung cancer spreads to the brain, liver, adrenal glands, and bones — areas a chest X-ray misses. PET-CT finds active disease elsewhere. EBUS samples mediastinal nodes without surgery. Brain MRI is standard because brain metastases are common. The multidisciplinary team at Jaipur Hospital combines all these tests for accurate staging.
Your next step at Jaipur Hospital
Staging investigations usually complete within one to two weeks. Your surgeon will discuss results at the tumour board meeting.
FAQ library
Questions and answers about lung cancer and nodule care
When you contact us
Get your assessment and plan
Contact Jaipur Hospital for an OPD consultation, in-house tests, a tumour board opinion, a cost estimate and cashless scheme help.
- A consultation with a pulmonologist (chest physician) in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Lung Cancer and Nodule Care: what to know
What lung nodules and lung cancer are
- nearly 1 out of every 3 Nodules on chest CT
- two-year Surveillance period
A pulmonary nodule is a spot on your lung that looks different from the surrounding tissue on an X-ray or CT scan. Radiologists see these nodules in nearly 1 out of every 3 chest CT scans.
They can be:
- Solid
- Hazy (called ground-glass opacity)
- A mix of both
Most lung nodules are benign (not cancerous). Nodules that stay the same size during a two-year surveillance period are not likely to be cancer. Lung cancer starts when abnormal cells in the lung grow out of control. A provider cannot tell by looking at a CT scan whether a nodule is cancerous — only a biopsy can diagnose cancer.
Symptoms of lung nodules and warning signs that need urgent care
- Cough that does not go away
- Coughing up blood
- Shortness of breath
- Chest pain
- Hoarseness
- Unexplained weight loss
Small lung nodules rarely cause symptoms. If a growth presses against your airway or is cancerous,
you might experience:
- Cough that does not go away
- Coughing up blood
- Shortness of breath
- Chest pain
- Hoarseness
- Unexplained weight loss
These symptoms need medical attention the same day. If you are already under follow-up for a nodule and notice new or worsening breathing difficulty, sudden chest pain, or coughing up blood, go to the emergency department without delay.
Causes of lung nodules and who is at higher risk
- Smoking history
- Personal history of smoking
- Secondhand smoke
- Exposure to secondhand smoke
- Workplace exposure
- Asbestos or radon exposure
- Family history
- Personal or family history of lung cancer
- Past chest radiation
- Previous radiation therapy to the chest
Infections, inhaled particles, inflammatory conditions, scarring and cancer can all cause pulmonary nodules. Infections, autoimmune diseases and cancer can also cause them.
Risk factors for lung cancer include:
- A history of smoking
- Exposure to secondhand smoke
- Occupational exposure to substances such as asbestos or radon
- A personal or family history of lung cancer
- Previous radiation therapy to the chest
Your provider uses these factors along with the nodule's size, shape and appearance to decide whether you need a biopsy or follow-up imaging.
How lung nodules and lung cancer are diagnosed
- Nodule found on imaging X-ray or CT scan
- Features assessed Size, edges, risk factors
- Tumour board review Multidisciplinary team
- Biopsy or follow-up CT-guided, EBUS, EUS, molecular testing
Most people find out they have a lung nodule after a screening test or an imaging test for an unrelated reason. Providers see nodules on imaging like X-rays or CT scans. They are usually noncancerous but your provider may have you get a biopsy or follow-up imaging.
Certain features help determine whether you need a biopsy — for instance, small nodules (smaller than 0.6 centimetres) and those with smooth edges are usually less likely to be cancerous. Your provider is likely to recommend a biopsy if a nodule is larger than 9 millimetres, or you have certain risk factors for lung cancer.
At Jaipur Hospital, a multidisciplinary tumour board with a pulmonologist, oncologist, thoracic surgeon, radiologist and pathologist reviews every case together. Biopsy options include CT-guided percutaneous biopsy for peripheral nodules and EBUS or EUS guided staging for mediastinal nodes. Molecular testing such as EGFR, ALK and ROS1 is done on the biopsy sample to guide targeted therapy or immunotherapy. Ensuring the biopsy sample is large enough prevents the need for a second procedure.
Non-surgical treatment options and when surgery is advised
Small, noncancerous lung nodules do not usually require treatment. If nodules are caused by an infection, you might need antibiotics or antifungal medications. Depending on your health history and the size of the nodule, your provider may recommend active surveillance with additional imaging in six to 12 months. If the nodule grows or causes symptoms, you may need surgery.
Surgery is the preferred treatment option for patients with early-stage non-small cell lung cancer. For advanced disease, systemic therapy is chosen based on molecular results. First-line therapy for advanced non-small cell lung cancer that lacks targetable mutations is platinum-based chemotherapy.
Among patients with a PD-L1 tumour proportion score of 50% or greater, pembrolizumab has replaced cytotoxic chemotherapy as the first-line treatment of choice. Osimertinib is an oral, third-generation EGFR tyrosine kinase inhibitor used for EGFR mutation-positive disease. Nivolumab is a PD-1 immune checkpoint inhibitor used after progression on chemotherapy.
In studies, adding pembrolizumab to chemotherapy resulted in significantly higher response rates and longer progression-free survival than chemotherapy alone. Osimertinib showed a median progression-free survival of 18.9 months compared with 10.2 months with standard EGFR-TKIs. Treatment-related adverse events of grade 3 or 4 were reported in 10% of patients receiving nivolumab and 54% receiving docetaxel in one trial. Your surgeon and oncologist will advise which approach suits you based on the tumour board recommendation.
Preparing for lung cancer surgery at Jaipur Hospital
Do
- List of allergies
- Insurance card
- Referral letters
Before surgery you will meet the surgical team and the anaesthetist. They review your imaging, biopsy report and lung function tests. Blood tests, an ECG and a chest X‑ray are usually done a few days before admission. If you take blood thinners, diabetes medicines or steroids, tell your surgeon so the dose can be adjusted. You will be asked to stop eating and drinking at least six hours before the operation.
Bring:
- Your current medicines
- A list of allergies
- Your insurance card
- Any referral letters
An attendant should stay with you during the hospital stay. The team will explain the planned procedure and answer your questions before you sign the consent form.
How lung cancer surgery is done at Jaipur Hospital
- Admission and preparation Ward, theatre gown, IV line, monitoring
- Operation Two to four hours
- Post-operative care ICU or high-dependency area overnight
On the day of surgery you are admitted to the ward, changed into a theatre gown and taken to the modular operation theatre. An intravenous line is placed and monitoring devices are attached. After anaesthesia the surgeon makes the planned incisions, performs the resection and places a chest drain to remove air and fluid.
The operation usually takes two to four hours. You are then moved to the intensive care unit or a high‑dependency area for overnight observation.
Risks and possible complications of lung cancer surgery
- Air leak
- Prolonged drainage from the lung
- Infection
- At the incision or inside the chest
- Bleeding
- May need a transfusion
- Irregular heart rhythms
- Can occur after surgery
All major chest surgery carries risks.
Common early complications include:
- Air leak from the lung (prolonged drainage)
- Infection at the incision or inside the chest
- Bleeding that may need a transfusion
- Irregular heart rhythms
Pain is expected and managed with epidural or patient‑controlled analgesia. Less common but serious risks are blood clots in the legs or lungs, pneumonia and respiratory failure that may need ventilator support. In studies of immunotherapy with nivolumab, grade 3 or 4 treatment‑related adverse events occurred in about 1 in 10 patients.
In a chemotherapy group receiving docetaxel, grade 3 or 4 events occurred in about 54% of patients. Your surgical team will discuss the risks that apply to your situation and the steps taken to reduce them.
Recovery and aftercare after lung cancer surgery
After surgery you stay in the hospital for four to seven nights. The chest drain is removed once the air leak stops and the lung stays expanded. You are encouraged to sit up, do breathing exercises and walk short distances from the first day. Pain is controlled with regular medication.
Before discharge you receive instructions on wound care, breathing exercises, activity limits and follow‑up dates. At home, avoid heavy lifting and strenuous activity for four to six weeks. Most people feel tired for several weeks; gradual increase in walking helps.
Call the hospital if you develop:
- Fever
- Increasing chest pain
- Sudden shortness of breath
- Redness or discharge from the wound
- Coughing up blood
Follow‑up visits include chest X‑rays and, later, CT scans to monitor healing and check for recurrence. If further treatment such as chemotherapy or radiation is advised, the oncology team will plan the schedule with you.
Results of lung cancer treatment in studies
Outcomes depend on the stage, cell type and molecular profile of the cancer. In studies of advanced non‑small‑cell lung cancer without targetable mutations, platinum‑based chemotherapy has been the standard first‑line treatment. For tumours with PD‑L1 expression of 50% or more, pembrolizumab has replaced chemotherapy as the preferred first‑line option.
In a phase 3 trial, median progression‑free survival was 10.3 months with pembrolizumab versus 6.0 months with chemotherapy. The hazard ratio for disease progression or death was 0.50. In another trial, median overall survival was 12.2 months with nivolumab and 9.4 months with docetaxel. The one‑year overall survival rate was 51% with nivolumab versus 39% with docetaxel.
For EGFR‑mutation‑positive advanced disease, osimertinib showed a median progression‑free survival of 18.9 months compared with 10.2 months with standard EGFR‑TKIs. The hazard ratio for progression or death was 0.46. These results come from groups of patients in clinical trials; individual outcomes vary.
The multidisciplinary tumour board at Jaipur Hospital uses this evidence along with your pathology and molecular results to recommend the treatment plan most likely to help you.
Cost and insurance for lung cancer care in Jaipur
A full course of treatment at Jaipur Hospital typically costs between ₹1,50,000 and ₹15,00,000. The final amount depends on the type of surgery, number of chemotherapy or immunotherapy cycles, targeted therapy drugs, radiation sessions, hospital stay and any intensive care needs.
Molecular testing such as next‑generation sequencing to identify EGFR, ALK, ROS1 and other mutations adds to the cost but guides the choice of targeted therapy or immunotherapy.
The hospital accepts:
- RGHS
- MAA Yojana
- CGHS
- A panel of private insurers and TPAs
The in‑house pharmacy and diagnostic laboratory mean most medicines and tests are available on site. Ask the billing office for an estimate based on your proposed treatment plan.