

General & Laparoscopic Surgery · Jaipur Hospital
Thyroid Surgery in Jaipur
Swelling or nodule in your neck? Get a clear assessment and a simple plan at Jaipur Hospital.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Operation time
- 1 to 3 hours
- Anaesthesia
- General anaesthesia
- Recovery
- Back to desk work in 1 to 2 weeks for most patients
- Price
- ₹60,000 to ₹1,80,000typical range in India; ask us for an estimate
A lump in your neck
You feel a swelling or have been told a nodule needs checking
A visible lump, difficulty swallowing, or a nodule found on a scan can cause worry about cancer and what surgery involves. You need to know if an operation is necessary and what it means for daily life.
-
Visible neck swelling
A lump you can see or feel that may grow over time.
-
Trouble swallowing or breathing
Pressure from a large goitre on the food pipe or windpipe.
-
Abnormal scan or biopsy result
A nodule flagged as suspicious on ultrasound or FNAC report.
-
Voice change or hoarseness
Nerve involvement suspected when voice alters without a cold.
Thyroid nodules are common, with a prevalence of 4–7% in the population.
Why Jaipur Hospital
You are worried about a scar on your neck, time off work, and whether your voice will sound the same afterwards.
Your care plan
Your first steps with us
- 1 Call or visit OPD for a surgeon consultation
- 2 Complete blood tests, ultrasound, and FNAC in-house
- 3 Review the surgical plan and cost estimate with your surgeon
- 4 Admit for surgery, recover 1 to 2 nights, then follow-up
How the operation is done
Under general anaesthesia, the surgeon makes a small cut in the neck crease, identifies and protects the nerves and parathyroid glands, and removes the required portion of the thyroid. The operation usually takes 1 to 3 hours.
-
Total thyroidectomy
The whole gland is removed; lifelong thyroid hormone tablets are needed afterwards.
-
Hemithyroidectomy
One lobe is removed; many patients keep enough thyroid function to avoid daily tablets.
-
Neck dissection
Lymph nodes are removed when cancer has spread to them, done during the same operation.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 3 General & Laparoscopic Surgery consultants
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
What studies show about thyroid surgery outcomes
-
1 to 2 weeks
Most patients return to desk work within one to two weeks after surgery.
-
about 1 in 10
Temporary voice change from nerve irritation occurs in about one in ten patients.
-
median 27 per cent
Temporary low calcium levels are seen in roughly one in four patients after total thyroidectomy.
If it is left untreated
If a suspicious nodule or cancer is left untreated, it can grow, spread to lymph nodes, or press on the windpipe and food pipe, making breathing and swallowing harder.
Life after treatment
Most people return to normal routines within a few weeks, with a small neck scar that fades over time.
-
Back to work
Most people resume desk work within one to two weeks.
-
Voice returns
Temporary hoarseness usually settles within a few weeks to six months.
-
Daily tablet if needed
After total thyroidectomy, a daily thyroid hormone tablet keeps levels normal.
-
Calcium supplements short-term
Calcium and vitamin D tablets are often given for a few weeks after surgery.



Frequently asked questions
Questions patients ask about thyroid surgery
What does thyroidectomy involve?
In short
Thyroidectomy at Jaipur Hospital is surgery to remove all or part of the thyroid gland. The operation takes one to three hours under general anaesthesia. You will stay in hospital for one to two nights. Our surgical team makes a small cut in the lower neck to reach the gland. The exact steps depend on how much tissue needs to be removed.
In detail
The surgeon identifies and protects the recurrent laryngeal nerves that control the voice box and the parathyroid glands that regulate calcium. In a total thyroidectomy the whole gland is removed and lifelong thyroid tablets are needed.
In a hemithyroidectomy only one lobe is taken out and many patients keep normal hormone levels. If cancer has spread to lymph nodes a neck dissection may be added. The wound is closed with dissolvable stitches and skin glue.
A common belief
Many people think the whole gland is always taken out, but a hemithyroidectomy removes only one lobe.
What actually happens
The extent depends on your diagnosis, not a fixed rule.
Your next step at Jaipur Hospital
After surgery you will be watched for bleeding and calcium levels. Most people return to desk work in one to two weeks. You will receive advice on calcium and vitamin D supplements if needed. Voice changes usually improve within weeks. A follow-up visit is scheduled around three weeks.
Which tests and scans do I need before thyroidectomy?
In short
Before thyroidectomy at Jaipur Hospital, you will need a neck ultrasound of the thyroid and lymph nodes, thyroid function tests (TSH, T3, T4), and usually a fine-needle aspiration biopsy if a nodule meets size and suspicion criteria. Blood tests for calcium, vitamin D, and bleeding profile are also done. Vocal cord assessment by laryngoscopy is recommended if you have voice changes, cancer with suspected spread, or previous neck surgery.
In detail
Guidelines specify ultrasound for all patients with suspected nodular disease. FNA indications follow EU-TIRADS size cut-offs: EU-TIRADS 5 over 10 mm, EU-TIRADS 4 over 15 mm, EU-TIRADS 3 over 20 mm.
If TSH is low, a thyroid scan may be done to check for functioning nodules. CT or MRI is only used if there is concern about extension into the chest or nearby structures. Preoperative calcium and vitamin D levels help predict hypocalcemia risk. The anaesthesia team will review your fitness for general anaesthesia.
A common belief
Patients often ask why they need so many tests for a 'simple' neck operation.
What actually happens
The ultrasound maps the nerves and lymph nodes. The biopsy confirms if it's cancer. Calcium and vitamin D levels predict who might need supplements after surgery. Skipping any of these increases the risk of surprises during or after the operation.
Your next step at Jaipur Hospital
Bring all previous imaging and biopsy reports to your preoperative visit. The surgeon may repeat ultrasound or biopsy if prior studies are incomplete. You will also have routine preoperative blood work and an ECG. The anaesthetist will see you before surgery. Plan to complete these tests a few days before your admission.
How painful is thyroid surgery and the early recovery?
In short
At Jaipur Hospital, thyroid surgery is done under general anaesthesia so you feel no pain during the operation. After surgery, most patients describe a sore throat and mild neck discomfort rather than severe pain. Regular pain tablets control this well, and the vast majority of patients do not need strong opioid medicines.
In detail
The breathing tube used during general anaesthesia often leaves a sore throat for a few days, especially when swallowing. The neck incision may feel tight or tender. Studies show most patients manage with simple pain relief such as paracetamol.
The collodion dressing on the wound can harden and cause a pulling sensation when you swallow or extend your neck, peaking around three weeks and fading over three to six months.
Seroma, a collection of clear fluid under the wound, can cause a feeling of fullness but usually resolves on its own. If a larger seroma forms, the team can aspirate it under sterile conditions.
A common belief
Patients often expect severe pain.
What actually happens
In reality, the discomfort is more like a bad cold with a tight neck. The dressing can feel stiff for a few weeks, but that is normal healing, not a complication.
Your next step at Jaipur Hospital
You will receive pain tablets before discharge. Take them regularly for the first two to three days, then as needed. Eat soft foods if swallowing is uncomfortable. Avoid heavy lifting for one week. Contact the hospital if pain suddenly worsens or you notice increasing neck swelling.
How long does recovery usually take after thyroid surgery?
In short
At Jaipur Hospital, most patients stay in hospital for one to two nights after thyroid surgery. You can return to desk work in one to two weeks. Full recovery, including wound healing and return to heavy activity, takes about two to three weeks. The scar continues to mature for 12 to 18 months.
In detail
You will be awake and able to eat and drink a few hours after surgery. Walking and normal light activity are encouraged the same evening. Heavy lifting, swimming, and soaking the wound are avoided for one week.
Temporary hoarseness usually improves within a few weeks but can take up to six months. Temporary low calcium is managed with supplements for at least 10 days.
The wound dressing hardens and peaks at three weeks, causing some tightness when swallowing, which fades over three to six months. Seroma may appear but often resolves without treatment. Nerve recovery, if injured, typically occurs between four and six weeks for transient injury.
A common belief
People often think they need weeks of bed rest.
What actually happens
In fact, walking and light activity start the same day. The main limits are heavy lifting for one week and waiting for hormone levels to stabilise over months.
Your next step at Jaipur Hospital
Plan for one to two weeks off desk work and two to three weeks before heavy exertion. Take calcium and vitamin D as prescribed. Attend the three-week follow-up for wound, voice, and calcium check. Use sunscreen on the scar after it heals.
What do my TSH, T3, and T4 results mean for thyroid surgery?
In short
TSH, T3, and T4 levels help your surgeon at Jaipur Hospital understand how your thyroid is working and guide the need for surgery. High or low levels can indicate overactive or underactive disease, while normal levels with a nodule may still need investigation. Your surgeon will explain your specific results at the consultation.
In detail
Thyroid function tests are part of the standard workup. A subnormal TSH suggests a hyperfunctioning nodule, which may be treated with radioiodine instead of surgery. Normal TSH with a suspicious nodule on ultrasound usually leads to a fine-needle aspiration biopsy to check for cancer.
After total thyroidectomy, you will need lifelong thyroid hormone replacement, and the dose is adjusted based on TSH levels checked every few months until stable. The surgeon uses these values along with ultrasound findings and biopsy results to decide the type and extent of surgery.
A common belief
Patients often think normal blood tests rule out surgery.
What actually happens
But a suspicious nodule with normal hormones may still need biopsy and possible removal.
Your next step at Jaipur Hospital
Bring your recent blood reports to your appointment. The surgeon will review TSH, T3, T4, and any antibody tests together with your ultrasound and biopsy results. This helps decide if surgery is needed and whether you will need hormone tablets afterward.
How will the surgeon decide whether an operation is necessary for my thyroid condition?
In short
The surgeon at Jaipur Hospital decides on surgery by reviewing your symptoms, ultrasound findings, biopsy results, thyroid function tests, and overall health. Surgery is usually recommended for confirmed or highly suspicious cancer, large goiters causing breathing or swallowing difficulty, overactive nodules not controlled by medicine, and indeterminate nodules that cannot be safely watched.
In detail
Guidelines list specific indications: Bethesda V or VI cytology, symptomatic benign nodules, compressive symptoms like dysphagia or dyspnea, toxic nodules, and nodules growing despite surveillance. For small, low-risk papillary microcarcinomas, active surveillance may be offered as an alternative.
Your surgeon also checks vocal cord function before surgery if you have voice changes or a high-risk cancer. The decision is made in a shared discussion with you, weighing the risks of surgery against the risks of observation.
A common belief
Some patients expect surgery for every nodule.
What actually happens
Many nodules are safely watched. Others assume a benign biopsy means no surgery ever. Large or growing benign nodules can still need removal for comfort or breathing.
Your next step at Jaipur Hospital
Bring all your reports, including ultrasound, biopsy, and blood tests, to the OPD consultation. The surgeon will explain the reasoning for or against surgery in your case. If surgery is advised, the type of operation and expected hospital stay will be outlined.
Why might my doctor recommend thyroidectomy?
In short
A doctor may recommend thyroidectomy at Jaipur Hospital for thyroid cancer, a large goitre causing swallowing or breathing difficulty, suspicious nodules on biopsy, or an overactive gland not controlled by medicines. The decision is based on your symptoms, scan results and fine needle aspiration findings. Surgery aims to remove the problem and prevent it from getting worse.
In detail
Guidelines list several situations where surgery is appropriate. These include nodules with Bethesda class V or VI cytology, indeterminate nodules not suitable for watchful waiting, compressive symptoms from a large goitre, and hyperthyroidism that does not respond to medical treatment.
Aesthetic concern from a visible neck swelling can also be a reason. The type of operation, total or partial, depends on the underlying condition and how much tissue is involved.
A common belief
Not every nodule needs surgery.
What actually happens
Many small or benign nodules are safely watched with regular ultrasounds. Surgery is chosen when the risk of leaving it is higher than the risk of the operation.
Your next step at Jaipur Hospital
Your surgeon will explain the specific reason in your case and what the alternatives are. You will have blood tests, a neck ultrasound and possibly a CT scan before a final plan is made. Most patients stay one to two nights and resume light activity within two weeks.
How should I prepare in the days before thyroidectomy?
In short
In the days before thyroidectomy at Jaipur Hospital, follow your surgeon's instructions on medicines. You may need to stop blood thinners or certain supplements a few days prior. Arrange for an attendant to stay with you in hospital. Prepare soft foods for the first few days at home. Stop smoking if possible, as it affects healing. Keep the neck area clean.
In detail
Evidence shows preoperative optimisation reduces complications. If you take thyroid hormone, continue the same dose unless your surgeon changes it. Blood thinners like aspirin or warfarin are usually stopped 5 to 7 days before surgery after consulting your cardiologist.
Herbal products that increase bleeding risk (garlic, ginkgo, ginseng) should be stopped two weeks prior. Vitamin D deficiency should be corrected if time permits, as low levels predict postoperative hypocalcemia. The anaesthetist will advise on your regular medicines on the morning of surgery.
A common belief
People often forget to stop supplements like garlic or ginkgo, which can increase bleeding.
What actually happens
Others stop their thyroid medicine on their own — this can cause problems. Vitamin D is rarely checked but low levels make low calcium after surgery more likely. A proper preoperative plan covers all of these.
Your next step at Jaipur Hospital
You will be admitted on the day of surgery or the evening before. Fast from midnight before the operation. Bring your medicines, reports, and insurance papers. Wear loose clothing with a front opening. The hospital provides gowns. Your attendant should be ready to help you after discharge. Confirm your admission time with the admissions desk.
What are the common side effects and the less common serious complications of thyroid surgery?
In short
At Jaipur Hospital, common side effects after thyroid surgery include a sore throat, mild hoarseness, temporary low calcium with tingling in the fingers or lips, and a small neck scar. Less common serious complications are bleeding that causes neck swelling or breathing difficulty, lasting voice change from nerve injury, and long-term low calcium needing ongoing supplements.
In detail
Studies show temporary voice change occurs in about one in ten patients and usually resolves in weeks. Lasting voice problems affect up to one in twenty-five.
Temporary low calcium happens in roughly twenty to thirty percent after total thyroidectomy; lasting low calcium is about one percent. Bleeding needing re-operation is under one percent. Infection is rare. Your surgeon identifies the recurrent laryngeal nerve and parathyroid glands during the operation to minimise these risks.
A common belief
People often worry most about the scar.
What actually happens
The bigger risks are calcium and nerve issues, which the surgical team actively prevents by identifying the nerve and parathyroids during every operation.
Your next step at Jaipur Hospital
You will be watched in hospital for one to two nights for bleeding and calcium levels. Take calcium and vitamin D tablets as prescribed. Report any tingling, muscle cramps, worsening hoarseness, neck swelling, or breathing trouble immediately. The scar fades over twelve to eighteen months.
Which symptoms are expected after thyroid surgery, and which need urgent medical attention?
In short
At Jaipur Hospital, expected symptoms after thyroid surgery include a sore throat for a few days, mild hoarseness that may last weeks, neck stiffness, and tingling in the fingers or around the lips from temporary low calcium. Urgent symptoms are difficulty breathing, stridor (high-pitched noise when breathing), rapidly increasing neck swelling, severe muscle cramps, or numbness that does not improve with extra calcium tablets.
In detail
The sore throat comes from the breathing tube and settles in two to three days. Hoarseness from nerve irritation usually improves in three to four weeks but can take six months.
Low calcium symptoms (tingling, cramps, Chvostek's or Trousseau's signs) typically appear twenty-four to forty-eight hours after surgery. Bleeding is most likely in the first six hours but can happen up to twenty-four hours.
A deep haematoma may not cause obvious swelling but can cause breathing trouble. Infection is rare but would show as increasing redness, heat, or pus at the wound.
A common belief
Patients often ignore tingling, thinking it will pass.
What actually happens
Low calcium can progress to dangerous heart rhythm changes. Treat tingling early with extra calcium and call the team if it does not settle in thirty minutes.
Your next step at Jaipur Hospital
Take prescribed calcium and vitamin D on schedule. If tingling occurs, take two extra calcium tablets; if it persists after thirty minutes, call the hospital.
For any breathing difficulty, neck swelling that grows, or stridor, go to the nearest emergency department or call the hospital immediately. Do not wait.
FAQ library
Questions and answers about thyroid surgery
When you contact us
Get your assessment and plan
Contact Jaipur Hospital for an OPD consultation, in-house tests, a clear explanation of options, and a cost estimate before you decide.
- A consultation with a general and laparoscopic surgeon in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Thyroid Surgery: what to know
What thyroid surgery is and how the condition develops
- Total thyroidectomy
- Whole gland removed
- Hemithyroidectomy
- One half removed
- Neck dissection
- Lymph nodes removed if cancer spread
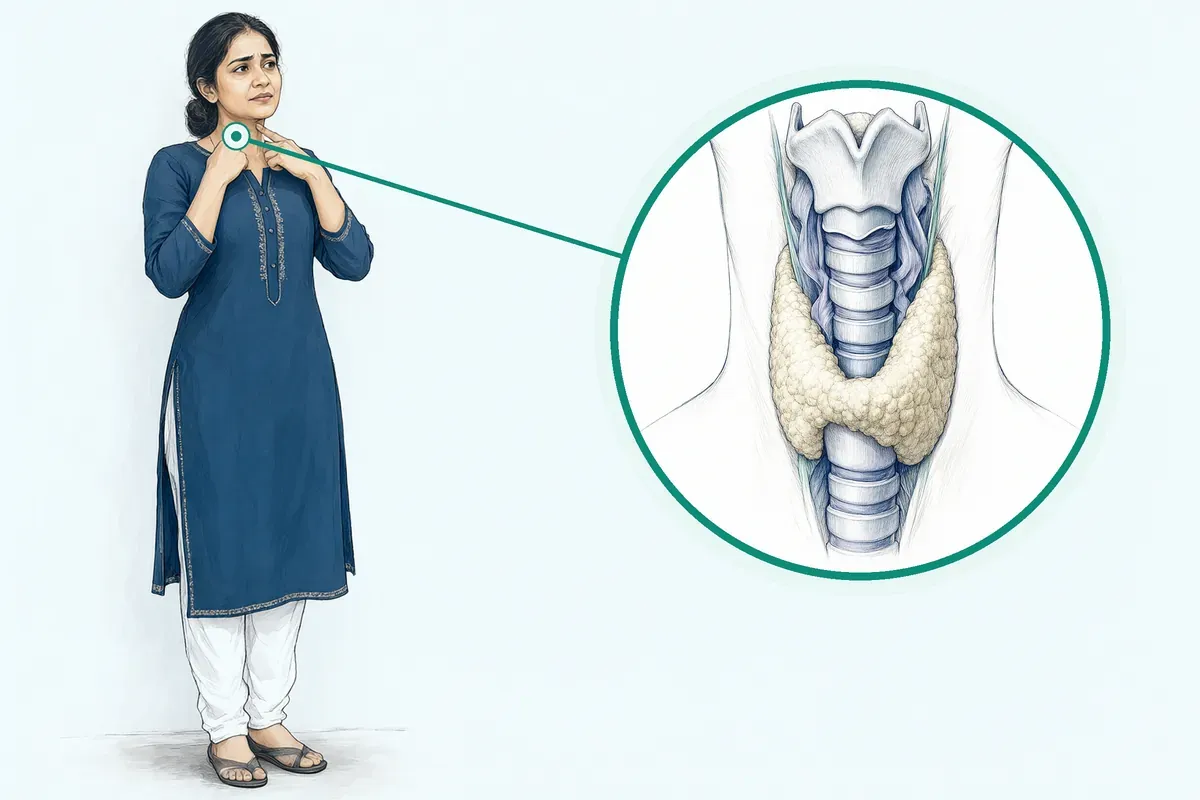
The thyroid is a butterfly-shaped gland in the front of the neck that makes hormones to control metabolism and other body functions. When this gland develops nodules, grows too large (goitre), or becomes cancerous, surgery may be needed to remove all or part of it. Thyroidectomy is the operation to remove the whole gland (total thyroidectomy) or one half (hemithyroidectomy). In some cases, nearby lymph nodes are also removed if cancer has spread to them.
Most thyroid nodules are harmless and cause no symptoms. They are often found by chance during scans for other reasons. Over time, some nodules grow large enough to press on the windpipe or food pipe, causing breathing or swallowing trouble. A small number of nodules turn out to be cancer. Papillary thyroid cancer is the most common type and usually has a favourable outlook.
Your surgeon will explain which operation suits you based on the size and type of the nodule, the biopsy result, and whether cancer is suspected or confirmed. The operation takes about one to three hours under general anaesthesia.
Symptoms and warning signs that need urgent care the same day
- Sudden neck swelling Keeps getting bigger
- Breathing difficulty Noisy or high-pitched breath
- Serious neck or chest feeling Something feels very wrong
- Numbness not improving After extra calcium tablets
- Fever or wound infection Pus or increasing pain
Many people with thyroid nodules feel nothing unusual.
When symptoms appear, they may include:
- A visible lump in the neck
- A feeling of pressure or tightness
- Difficulty swallowing
- A change in voice such as hoarseness
A very large goitre can press on the windpipe and cause noisy breathing or shortness of breath, especially when lying flat.
After surgery, some throat soreness and mild hoarseness are common for a few days because of the breathing tube used during anaesthesia. Temporary numbness or tingling around the lips, fingertips, or toes can appear 24 to 48 hours after surgery if blood calcium drops. This usually settles with calcium and vitamin D tablets.
Contact the hospital or go to the emergency department on the same day if you notice:
- Sudden swelling in the neck that keeps getting bigger
- Difficulty breathing, noisy breathing (stridor), or a high-pitched voice
- A feeling that something is seriously wrong in the neck or chest
- Numbness or tingling that does not improve after taking extra calcium tablets as advised
- Fever, increasing wound pain, or pus from the incision
These can be signs of bleeding, airway pressure, or low calcium that need immediate attention.
Causes and who is at higher risk of needing thyroid surgery
- Iodine deficiency
- Can cause goitre formation
- Radiation exposure
- Childhood radiation to head, neck or chest
- Family history
- Thyroid disease or genetic syndromes
- Gender and age
- Women more often diagnosed; risk rises with age
The exact cause of thyroid nodules is not always clear. Iodine deficiency in the diet can contribute to goitre formation. Radiation exposure to the head, neck, or chest during childhood increases the risk of thyroid nodules and cancer later in life. Women are diagnosed with thyroid nodules more often than men. The chance of finding nodules rises with age.
A family history of thyroid disease or certain genetic syndromes can raise the risk. Graves' disease (an overactive thyroid) and large multinodular goitres that cause compressive symptoms are common reasons for surgery. Nodules that look suspicious on ultrasound or biopsy (Bethesda class V or VI) are usually operated on.
Nodules with indeterminate biopsy results (class III or IV) may be watched or operated on depending on their features and your preference.
If cancer is found, the risk of it spreading to lymph nodes is higher with larger tumours or certain aggressive features. Your surgical team will assess all these factors before recommending an operation.
How thyroid conditions are diagnosed: examination and tests
- Clinical neck examination Doctor feels for lumps and checks voice
- Blood tests TSH, T3, T4 and sometimes calcitonin
- Neck ultrasound Shows nodule size, shape and lymph nodes
- FNA biopsy Cells taken under ultrasound guidance
The first step is a clinical examination of the neck. The doctor feels for lumps and checks for any voice change. Blood tests measure thyroid hormone levels (TSH, T3, T4) and sometimes calcitonin. If TSH is low, a thyroid scan may be done to see if a nodule is overactive.
Ultrasound of the neck is the main imaging test. It shows the size, shape, and internal features of every nodule and checks the lymph nodes on both sides of the neck. Each nodule is given a risk score (EU-TIRADS) that guides the next step. For example, a high-risk nodule larger than 10 mm usually needs a needle biopsy.
Fine-needle aspiration (FNA) biopsy takes a small sample of cells from the nodule under ultrasound guidance. The result is reported using the Bethesda system, which ranges from non-diagnostic (class I) to malignant (class VI). If the first sample is inadequate or shows indeterminate cells (class III), a repeat biopsy may be offered. Molecular testing on the biopsy sample can sometimes help decide whether surgery is needed.
CT or MRI scans are not routine. They are used only when the goitre extends behind the breastbone or when cancer spread to nearby structures must be assessed. Vocal cord movement is checked before surgery if you have voice symptoms, a large cancer, or previous neck surgery.
Treatment options without surgery and when thyroid surgery is advised
Do
- Cancer confirmed or suspected
- Indeterminate biopsy not suitable for surveillance
- Benign nodule causing compressive symptoms
- Large goitre extending into chest
- Hyperthyroidism not controlled with medicines
- Cosmetic concern from visible neck swelling
Not every thyroid nodule needs an operation. Small, benign-looking nodules that cause no symptoms can be watched with repeat ultrasounds every 6 to 12 months for high-risk nodules, or every 1 to 5 years for lower-risk ones. Pure or mostly fluid-filled cysts can be drained or treated with ethanol ablation (injection of alcohol) instead of surgery. Solid benign nodules that cause pressure symptoms may be treated with thermal ablation (heat) as an alternative.
Radioactive iodine (RAI) is an option for overactive solitary nodules or for multinodular goitre when surgery is not suitable. Thyroid hormone tablets are not recommended to shrink nodules in people with normal thyroid function. Iodine or selenium supplements help only if a deficiency is proven.
Surgery is advised when:
- Cancer is confirmed or strongly suspected on biopsy (Bethesda V or VI)
- A nodule with indeterminate biopsy (class III or IV) is not suitable for active surveillance
- A benign nodule or goitre causes compressive symptoms such as difficulty swallowing, breathing trouble, or persistent hoarseness
- A large goitre extends into the chest (retrosternal)
- Hyperthyroidism is not controlled with medicines or RAI is declined or unsuitable
- Cosmetic concern from a visible neck swelling that bothers you
For very small papillary cancers (microcarcinomas), active surveillance without immediate surgery is a recognised option in selected patients. Your surgeon will discuss the benefits and risks of each approach so you can decide together.
Preparing for thyroid surgery
Your surgeon will ask for blood tests to check thyroid hormone levels, calcium and parathyroid hormone. A neck ultrasound and, if needed, a CT or MRI scan help plan the operation. Vocal cord movement is usually checked before surgery with a simple scope test. Tell your doctor about every medicine you take, especially blood thinners, and any supplements.
You may be asked to stop blood thinners a few days before the operation. If you take thyroid hormone, keep taking it unless your surgeon tells you to change the dose. Fasting starts at midnight before surgery; you may have a sip of water with essential tablets.
Bring your test reports, insurance cards, a list of medicines, loose clothing with a wide neck, and an attendant to stay with you overnight.
How thyroid surgery is done
Whole gland removed
- Total thyroidectomy
Half gland removed
- Hemithyroidectomy
Lymph nodes removed
- Neck dissection
The operation is done under general anaesthesia. You are completely asleep and a breathing tube protects your airway. The surgeon makes a cut in the lower neck, usually in a skin crease. The choice of operation depends on your diagnosis.
- Total thyroidectomy: the whole gland is removed. Lifelong thyroid hormone tablets are needed afterwards.
- Hemithyroidectomy (lobectomy): one half of the gland is removed. About 60 to 70 percent of patients with half a normal gland left do not need hormone tablets.
- Neck dissection: lymph nodes around the thyroid are removed when cancer has spread to them.
The surgeon identifies the recurrent laryngeal nerves and the parathyroid glands during the operation to protect them. The cut is closed with dissolvable stitches and skin glue. The operation usually takes one to three hours.
Risks and possible complications of thyroid surgery
- 20 to 30 percent after total thyroidectomy Temporary low calcium
- 1 to 3 percent beyond six months Long-lasting low calcium
- About 1 in 10 patients Temporary voice problems
- Up to 1 in 25 patients Longer-lasting voice problems
- 0.1 to 1.1 percent Bleeding or haematoma
- Far less than 1 percent Infection
Thyroid surgery is generally safe but it is a major operation. The two most common early complications are low blood calcium and recurrent laryngeal nerve injury.
Low blood calcium (hypocalcemia) happens when the parathyroid glands are temporarily stunned or injured. In studies, temporary low calcium occurs in about 20 to 30 percent of patients after total thyroidectomy. It is less common after hemithyroidectomy. Symptoms include numbness or tingling around the lips, hands and feet, usually appearing 24 to 48 hours after surgery.
Calcium and vitamin D tablets are given to treat it. Long-lasting low calcium needing treatment beyond six months is reported in about 1 to 3 percent of cases.
Recurrent laryngeal nerve injury can cause voice change. Temporary voice problems occur in about 1 in 10 patients. Longer-lasting voice problems are seen in up to 1 in 25 patients. The nerve can be injured by stretching, pressure or heat as well as cutting. Bilateral nerve injury is rare, less than 0.1 percent, and is a life-threatening emergency.
Bleeding or haematoma occurs in about 0.1 to 1.1 percent of cases. Most bleeding happens in the first six hours after surgery. A drain may be placed and is usually removed the next day. Infection is uncommon, reported in far less than 1 percent of operations.
A fluid collection (seroma) can form under the wound; small ones absorb on their own, larger ones may need drainage. Scarring varies; some people develop thickened scars. Difficulty swallowing can occur, especially after more extensive surgery.
Recovery and aftercare after thyroid surgery
After the anaesthetic wears off you can have sips of water and light food. Most patients stay one to two nights in hospital so the team can watch for bleeding, breathing difficulty and calcium levels. You will be encouraged to walk the same evening. Pain is usually mild; most patients do not need strong painkillers.
A sore throat from the breathing tube is common for a few days. Soft foods may be easier to swallow at first.
Before discharge you will get instructions on calcium and vitamin D tablets if needed. If you had a total thyroidectomy, thyroid hormone tablets start soon after surgery; the dose is based on weight and adjusted by blood tests every few weeks until stable.
At home, avoid heavy lifting, swimming and soaking the wound for one week. You can return to desk work in one to two weeks. The scar may feel tight for a few weeks and fades over 12 to 18 months.
Call the hospital or your surgeon if you notice: swelling in the neck that keeps growing, difficulty breathing or a high-pitched noisy breath, numbness or tingling that does not improve with extra calcium tablets, fever above 38°C, or increasing wound redness or discharge. A follow-up appointment is usually scheduled around three weeks after surgery.
Results of thyroid surgery
For thyroid cancer, surgery is the main treatment. Papillary thyroid cancer, the most common type, has a 5-year disease-specific survival above 98 percent and 10-year overall survival approaching 90 percent.
In studies, total thyroidectomy with prophylactic central neck dissection lowered the risk of cancer coming back in the neck (4.7 percent vs 8.6 percent) but increased temporary low calcium (26 percent vs 10.8 percent). Whether to do the extra dissection is decided case by case.
For benign nodules or goitre, surgery removes the pressure symptoms such as difficulty swallowing or breathing. In studies of endoscopic approaches, complete removal was achieved with good cosmetic results.
If the whole thyroid is removed, lifelong thyroid hormone replacement is needed. If half is removed, many patients do not need tablets. Calcium and vitamin D supplements are usually temporary. Voice changes from nerve injury recover in most cases within months; further treatment is not usually considered before six months.
Cost and insurance for thyroid surgery in Jaipur
The typical price range for thyroidectomy in India is ₹60,000 to ₹1,80,000. The final cost depends on the type of operation (conventional open, endoscopic or transoral), the room category you choose, the surgeon's fees, and whether additional procedures such as neck dissection are needed. Jaipur Hospital is a NABH-accredited multispeciality hospital with modular operation theatres and 24-hour laboratory and imaging.
The hospital accepts RGHS, MAA Yojana, CGHS and a panel of private insurers and TPAs. Ask the admissions desk for an estimate based on your planned procedure and room type.