

ENT (Ear, Nose and Throat) · Jaipur Hospital
Snoring and Sleep Surgery in Jaipur
Loud snoring and disturbed sleep leave you exhausted. Jaipur Hospital offers clear evaluation, sleep studies, and surgical care plans.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Operation time
- 1 to 3 hours
- Anaesthesia
- General anaesthesia
- Recovery
- 2 to 3 weekshypoglossal stimulator 4 to 6 weeks
- Price
- ₹80,000 to ₹2,50,000 (soft palate/nasal)₹10,00,000 to ₹18,00,000 (hypoglossal nerve stimulation)typical range in India; ask us for an estimate
Waking up tired every day
Loud snoring and broken nights
You wake up gasping, with a dry mouth and heavy fatigue. Loud snoring disturbs your family, while daytime drowsiness affects your work and daily safety.
-
Choking sounds at night
Breathing stops briefly during sleep as throat tissues collapse, causing gasping and frequent awakenings.
-
Heavy daytime sleepiness
Broken sleep patterns leave you feeling exhausted, irritable, and sleepy during routine daytime activities.
-
Difficulty with CPAP
Mask discomfort, skin irritation, or nasal blockage can make keeping a breathing mask on all night difficult.
-
Disturbed family rest
Persistent heavy snoring can disturb your spouse and family, causing worry and strained household sleep routines.
Obstructive sleep apnea is characterised by recurrent complete and partial upper airway obstructive events, resulting in intermittent hypoxemia, autonomic fluctuation, and sleep fragmentation.
Why Jaipur Hospital
You may worry about the discomfort of throat surgery, the cost, or taking weeks away from your work.
Your care plan
Your first steps with us
- 1 Consult your surgeon in the OPD for a sleep history assessment.
- 2 Complete diagnostic sleep testing and imaging in our in-house laboratory.
- 3 Undergo surgery in our modular operation theatre under general anaesthesia.
- 4 Recover at home over two to three weeks with scheduled follow-up visits.
Surgical procedures for airway obstruction
Procedures typically take 1 to 3 hours under general anaesthesia. Patients usually stay 1 to 2 nights in the hospital, with recovery taking 2 to 3 weeks.
-
Uvulopalatopharyngoplasty (UPPP)
Your surgeon will discuss removing palate and tonsil tissue to widen the airway for retropalatal obstruction.
-
Radiofrequency ablation of palate/tongue base
Your surgeon will discuss radiofrequency energy to stiffen tissues and reduce volume in the palate or tongue base.
-
Nasal obstruction correction
Your surgeon will discuss septoplasty, turbinate reduction, or valve repair to correct nasal obstruction and support airflow.
-
Hypoglossal nerve stimulation
Your surgeon will discuss an implantable neurostimulator for moderate-severe obstructive sleep apnea when CPAP is not tolerated.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 2 ENT (Ear, Nose and Throat) consultants
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
Clinical findings in sleep apnea care
-
40% to 60%
In clinical studies, between 40% and 60% of sleep apnea patients fail or are intolerant to CPAP therapy.
-
68% decrease
In a trial of upper-airway stimulation, median apnea-hypopnea index scores decreased 68% at 12 months.
-
40% to 80%
Sleep apnea prevalence reaches 40% to 80% among patients diagnosed with hypertension, heart failure, and coronary artery disease.
If it is left untreated
Leaving sleep apnea untreated carries health risks. Stroke, hypertension, and coronary artery disease are associated with sleep apnea. In middle-aged adults, untreated sleep apnea is also associated with increased cardiovascular mortality.
Expectations after airway surgery
Surgical care aims to open physical obstructions in the upper airway, helping patients work toward quieter nights and steadier daytime energy.
-
Smoother nighttime breathing
Most people notice fewer choking awakenings as enlarged tissues are reduced or supported by surgical treatment.
-
Improved daytime alertness
Patients usually report better energy and less daytime drowsiness once sleep fragmentation begins to settle.
-
Better household rest
Loud, disruptive snoring typically reduces, allowing both you and your attendant or family to rest comfortably.


Frequently asked questions
Questions patients ask about snoring and sleep surgery
Which problems are assessed under snoring and sleep surgery?
In short
At Jaipur Hospital, snoring and sleep surgery evaluates obstructive sleep apnoea, chronic snoring, and upper airway obstruction. The assessment covers retropalatal collapse, tongue base obstruction, nasal blockage, and multilevel airway narrowing. Your surgeon reviews sleep study results, clinical examination, and drug-induced sleep endoscopy findings to identify the exact sites of obstruction.
In detail
Obstructive sleep apnoea is characterised by recurrent complete and partial upper airway obstructive events resulting in intermittent hypoxemia and sleep fragmentation. The evaluation identifies whether obstruction occurs at the soft palate, tongue base, nasal passages, or multiple levels simultaneously.
Evidence shows OSA prevalence is as high as 40% to 80% in patients with hypertension, heart failure, coronary artery disease, and atrial fibrillation.
Drug-induced sleep endoscopy replicates sleep with propofol infusion to visualise the pattern of collapse, distinguishing flat anterior-posterior collapse from concentric collapse, which affects treatment eligibility. The assessment also considers body mass index, age, and comorbid conditions such as cardiovascular disease and metabolic syndrome.
A common belief
Many people think snoring is just noise, but evidence shows OSA links to hypertension, heart failure, and stroke.
What actually happens
A proper assessment maps the exact collapse pattern, not just symptoms.
Your next step at Jaipur Hospital
You will need a recent sleep study (polysomnography or home sleep apnoea test) and an OPD consultation with our ENT surgeon. The surgeon may recommend drug-induced sleep endoscopy to map your airway collapse pattern. Based on findings, a treatment plan is discussed within one to two visits.
How will the doctor decide which tests I need?
In short
The doctor at Jaipur Hospital decides tests based on your symptoms, clinical examination, and risk factors. A comprehensive sleep evaluation guides the choice between polysomnography and home sleep apnoea testing. Drug-induced sleep endoscopy is added if surgery is being considered to visualise the collapse pattern.
In detail
Guidelines recommend polysomnography for patients with significant cardiorespiratory disease, potential respiratory muscle weakness, awake hypoventilation, chronic opioid use, history of stroke, or severe insomnia.
Home sleep apnoea testing with a technically adequate device may be used for uncomplicated adults with signs of moderate to severe OSA. If a single home test is negative, inconclusive, or technically inadequate, polysomnography is performed.
A split-night protocol may be used during polysomnography when clinically appropriate. If clinical suspicion remains after a negative polysomnogram, a second study can be considered.
Drug-induced sleep endoscopy replicates sleep with propofol infusion to identify flat anterior-posterior or concentric palate collapse, which determines surgical eligibility, especially for hypoglossal nerve stimulation.
A common belief
Patients often expect one test for everyone.
What actually happens
In reality, guidelines match the test to your medical complexity. Home tests can miss OSA in people with heart failure, stroke, or opioid use. A negative home test does not rule out OSA; polysomnography is then needed. Sleep endoscopy is only done when surgery is a real option.
Your next step at Jaipur Hospital
Expect an OPD consultation with airway examination and symptom review. The doctor will order the appropriate sleep study based on your comorbidities. If the study confirms moderate to severe OSA and you are CPAP intolerant or have anatomical obstruction, drug-induced sleep endoscopy will be scheduled. Results are usually available within a week.
How soon should I expect improvement after snoring and sleep surgery?
In short
Improvement after snoring and sleep surgery at Jaipur Hospital depends on the procedure performed. For soft palate or nasal surgery, breathing often improves within two to three weeks as swelling settles. Hypoglossal nerve stimulation requires device activation one month after implantation, followed by gradual titration over several weeks. Your surgeon will explain the expected timeline for your specific operation.
In detail
Soft palate procedures such as UPPP or radiofrequency ablation involve tissue healing that typically takes two to three weeks; patients usually notice reduced snoring and better airflow once the throat swelling resolves. Nasal surgery like septoplasty or turbinate reduction follows a similar recovery.
For hypoglossal nerve stimulation, evidence shows the device is activated about one month after surgery and settings are adjusted over the next month, with a titration sleep study to fine-tune efficacy. In studies, the apnoea-hypopnoea index decreased significantly by 12 months. Individual response varies based on anatomy, body mass index, and adherence to post-operative care.
A common belief
Many patients expect instant results, but tissue healing and device programming take time.
What actually happens
CPAP users may need to pause therapy briefly after surgery, and the full benefit of nerve stimulation builds gradually over months, not days.
Your next step at Jaipur Hospital
Plan for a follow-up visit within the first week after discharge, then as advised by your surgeon. Keep the surgical site clean, take prescribed pain relief, and avoid heavy exertion for two to three weeks. For hypoglossal stimulation, attend all activation and titration appointments. If you use CPAP, discuss when to restart it.
How is an autoimmune condition confirmed?
In short
Autoimmune conditions are confirmed through a combination of clinical assessment, blood tests for specific autoantibodies, and inflammation markers, interpreted by a specialist at Jaipur Hospital. No single test gives the diagnosis; the doctor correlates your symptoms, examination findings, and laboratory results over time. A rheumatology consultation is usually required for definitive diagnosis and classification.
In detail
Diagnosis relies on recognised classification criteria that include symptom patterns, physical signs, and laboratory abnormalities. Common blood tests include antinuclear antibody (ANA), rheumatoid factor (RF), anti-cyclic citrullinated peptide (anti-CCP), extractable nuclear antigens (ENA), and disease-specific antibodies such as anti-dsDNA for lupus or ANCA for vasculitis.
Inflammation markers like C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) support the presence of active inflammation but are not specific. Imaging such as ultrasound or MRI may show joint erosions or organ involvement. The specialist excludes infections, malignancies, and other mimics before confirming an autoimmune diagnosis.
A common belief
Many people think a positive ANA alone means lupus, but ANA can be positive in healthy people and in other illnesses.
What actually happens
The pattern of symptoms and specific antibodies matter more than one isolated result.
Your next step at Jaipur Hospital
If you have persistent joint pain, unexplained fever, rash, or fatigue, ask your physician for a rheumatology referral. Bring any previous blood reports and imaging. The rheumatologist may repeat or extend antibody panels and order baseline organ function tests. Early diagnosis allows timely treatment to prevent damage.
How can I decide whether to seek advice about snoring surgery evaluation?
In short
Consider a surgical evaluation if you have loud, habitual snoring that disturbs others, witnessed breathing pauses during sleep, excessive daytime sleepiness despite adequate sleep time, or if you have tried and cannot tolerate continuous positive airway pressure (CPAP) therapy. Jaipur Hospital offers a structured assessment to determine whether surgery is appropriate for you. Surgery is usually recommended when non-surgical treatments fail or when anatomical obstructions are significant.
In detail
The decision starts with a clinical history, examination of the upper airway, and a sleep study (polysomnography or home sleep apnoea test) to confirm obstructive sleep apnoea and its severity.
Evidence shows that surgical intervention for obstructive sleep apnoea is usually recommended when non-surgical treatments such as CPAP or oral appliance therapy fail to provide sufficient symptom relief, and that 40 to 60 percent of patients fail or are intolerant to CPAP.
If the sleep study confirms moderate to severe apnoea and you cannot use CPAP, or if drug-induced sleep endoscopy shows a correctable anatomical collapse, surgery may be offered.
Options include uvulopalatopharyngoplasty, radiofrequency ablation, nasal surgery, tongue base reduction, or hypoglossal nerve stimulation, depending on the site and pattern of obstruction.
A common belief
Many people think surgery is a first step.
What actually happens
In practice, surgery is usually considered only after CPAP or oral appliances have been tried and failed, or when a clear anatomical blockage is found.
Your next step at Jaipur Hospital
Book a consultation with the otolaryngology team at Jaipur Hospital. Bring any previous sleep study reports. The surgeon will review your history, examine your airway, and advise whether further testing or a surgical option is suitable for your situation.
Could the problem affect hearing, balance, breathing, speech, or swallowing?
In short
Obstructive sleep apnoea itself does not directly impair hearing or balance. It affects breathing during sleep and can cause daytime sleepiness. Surgery on the palate, tongue base or nose may temporarily change speech resonance, swallowing comfort or nasal airflow. Jaipur Hospital counsels every patient on these expected short-term changes before any procedure.
In detail
Evidence shows OSA is a breathing disorder during sleep. Nasal surgery can improve nasal breathing and CPAP compliance. Palate surgery (UPPP) may cause temporary velopharyngeal insufficiency, leading to nasal regurgitation or hypernasal speech for a few weeks. Tongue base reduction can cause short-term swallowing discomfort.
Hypoglossal nerve stimulation does not alter speech or swallowing. Hearing and balance are not affected by these procedures. The team monitors recovery closely.
A common belief
People worry about long-term voice loss.
What actually happens
In practice, lasting speech or swallowing problems are rare and most patients return to normal within a month.
Your next step at Jaipur Hospital
If you notice persistent voice change beyond three weeks, painful swallowing that prevents eating, or new nasal blockage after healing, contact the hospital. A follow-up endoscopy may be arranged. Most changes resolve with time and speech therapy if needed.
Which symptoms should prompt me to see a specialist?
In short
At Jaipur Hospital, you should see a specialist if you have loud habitual snoring, witnessed breathing pauses during sleep, excessive daytime sleepiness, unrefreshing sleep, morning headaches, or nocturia. Excessive daytime sleepiness is suggested as the most important symptom of OSA. These symptoms, especially with obesity, hypertension, or atrial fibrillation, warrant a sleep evaluation.
In detail
Obstructive sleep apnoea is often underrecognised and undertreated. Approximately 34% and 17% of middle-aged men and women respectively meet diagnostic criteria for OSA. Sleep disturbances are common and underdiagnosed among middle-aged and older adults.
Only a fraction of subjects with AHI >5 report daytime sleepiness, and studies show no relationship between daytime sleepiness and sleep apnoea in some women. Cardiovascular guidelines recommend screening for OSA in patients with resistant hypertension, pulmonary hypertension, and recurrent atrial fibrillation.
Patients with nocturnally occurring angina, myocardial infarction, arrhythmias, or appropriate ICD shocks may be especially likely to have comorbid sleep apnoea. The presence of metabolic syndrome also indicates very high prevalence of moderate to severe OSA.
A common belief
Many ignore snoring as harmless, but evidence links OSA to resistant hypertension, atrial fibrillation, and heart failure.
What actually happens
Daytime sleepiness may be absent, especially in women, so cardiovascular risk factors matter as much as symptoms.
Your next step at Jaipur Hospital
If you notice these symptoms, schedule an OPD visit with our ENT or pulmonology department. Bring any previous sleep study reports. The doctor will take a focused history, examine your upper airway, and may order polysomnography or home sleep apnoea testing. Early evaluation helps prevent long-term cardiovascular risks.
How will the results change my care plan?
In short
At Jaipur Hospital, sleep study results directly shape your care plan. The apnoea-hypopnoea index severity, oxygen desaturation index, and sleep architecture determine whether conservative management, CPAP, oral appliance, or surgery is recommended. Drug-induced sleep endoscopy findings further guide surgical technique selection and hypoglossal nerve stimulation eligibility.
In detail
Evidence shows CPAP significantly reduces snoring and daytime sleepiness and improves quality of life. However, 40-60% of patients fail or are intolerant to CPAP.
For moderate to severe OSA with AHI 15-65, BMI 35 or less, and less than 25% central apnoeas, hypoglossal nerve stimulation is an option if CPAP fails. Concentric collapse on DISE excludes hypoglossal stimulation.
UPPP addresses retropalatal obstruction; nasal surgery improves CPAP compliance; tongue base reduction targets tongue collapse. Multilevel surgery combines approaches for multilevel collapse. Follow-up sleep testing assesses treatment effectiveness. The median AHI at 12 months decreased 68% from 29.3 to 9.0 events per hour in stimulation studies.
- The median AHI at 12 months decreased 68% from 29.3 to 9.0 events per hour in stimulation studies.
A common belief
Many assume a sleep study just confirms OSA.
What actually happens
In reality, the collapse pattern on DISE determines which surgery works. Concentric collapse rules out hypoglossal stimulation. CPAP failure rates of 40-60% mean surgery planning often follows the test results.
Your next step at Jaipur Hospital
After your sleep study, the surgeon reviews results with you in a follow-up OPD visit. If AHI confirms moderate to severe OSA, CPAP trial is usually first-line. If CPAP fails or anatomy favours surgery, DISE is scheduled. A multidisciplinary discussion may occur for complex cases. Treatment starts within weeks of decision.
What should I do if symptoms persist or worsen after snoring and sleep surgery?
In short
If snoring, breathing pauses, or daytime sleepiness persist or worsen after snoring and sleep surgery at Jaipur Hospital, contact your surgical team promptly. Some swelling and throat discomfort are normal in the first two to three weeks, but new or increasing difficulty breathing, severe pain, bleeding, or fever need urgent assessment. Your surgeon will decide if further evaluation or a repeat sleep study is required.
In detail
After soft palate or nasal surgery, temporary swelling can mask the final result for several weeks; however, persistent obstruction beyond the expected healing period may indicate residual tissue collapse or scarring.
For hypoglossal nerve stimulation, the device is activated one month post-operatively and titrated over the following month; if the apnoea-hypopnoea index remains elevated after titration, the stimulation parameters may need adjustment or additional procedures considered.
Evidence shows that in studies the median AHI decreased by 68% at 12 months, but individual outcomes vary. Weight gain, alcohol use, or untreated nasal allergy can also limit improvement. A follow-up sleep study is the standard way to objectively assess treatment effectiveness.
- Evidence shows that in studies the median AHI decreased by 68% at 12 months, but individual outcomes vary.
A common belief
Some patients wait months hoping things will improve on their own, but persistent obstruction usually means the anatomy still needs attention or the device settings need change.
What actually happens
A repeat sleep study gives the objective data your surgeon needs to decide the next step.
Your next step at Jaipur Hospital
Attend all scheduled post-operative reviews. Keep a symptom diary noting snoring loudness, witnessed apnoeas, and daytime sleepiness. Avoid alcohol and sedatives before sleep. If you experience sudden worsening of breathing, severe throat bleeding, or high fever, go to the emergency department.
For ongoing concerns, book a consultation at Jaipur Hospital so your surgeon can arrange a repeat sleep study or adjust your treatment plan.
What do antibody tests and inflammation markers mean in autoimmune disease?
In short
Antibody tests and inflammation markers help support the diagnosis and monitor activity of autoimmune conditions at Jaipur Hospital. A positive autoantibody such as ANA, RF, anti-CCP, or anti-dsDNA suggests an autoimmune process, but must be interpreted alongside symptoms. CRP and ESR reflect the level of inflammation but are not specific to any one disease.
In detail
Each antibody has a different diagnostic weight. For example, anti-CCP is highly specific for rheumatoid arthritis, while anti-dsDNA is more specific for systemic lupus erythematosus. ANA is sensitive but not specific; a positive result can occur in infections, medications, or healthy individuals.
ENA panels help differentiate overlap syndromes. CRP and ESR rise with inflammation from any cause, including infection or injury, so they are used to track disease activity and treatment response rather than to diagnose. Serial measurements over time are more informative than a single value. Your rheumatologist correlates these results with clinical findings to guide therapy.
A common belief
Patients often panic over a positive ANA or a high CRP.
What actually happens
Neither is a diagnosis by itself. The rheumatologist looks at the whole picture — symptoms, examination, and trends in repeated tests — not just one number.
Your next step at Jaipur Hospital
Do not start or stop any medication based on a single lab result. Discuss every report with your rheumatologist, who will decide if treatment needs adjustment. Repeat testing is usually done at each follow-up visit to monitor trends. Keep a file of all results for reference.
FAQ library
Questions and answers about snoring and sleep surgery
When you contact us
Consult our ENT surgical team in Jaipur
Book an OPD appointment at Jaipur Hospital to review your sleep symptoms and discuss your surgical treatment options.
- A consultation with an ENT surgeon in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Snoring and Sleep Surgery: what to know
What is obstructive sleep apnea and how does it happen
- Airway collapse
- Throat muscles relax and tissues block airflow
- Broken sleep
- Brief awakenings reopen the airway many times
- Health strain
- Oxygen drops and sleep fragmentation stress the heart
Obstructive sleep apnea, often called OSA, is an underdiagnosed condition. During sleep, repeated complete or partial blockages occur in your upper breathing passages. These repeated events lead to broken sleep, sudden drops in oxygen levels in the blood, and shifts in body functions. The condition carries substantial health risks for your body.
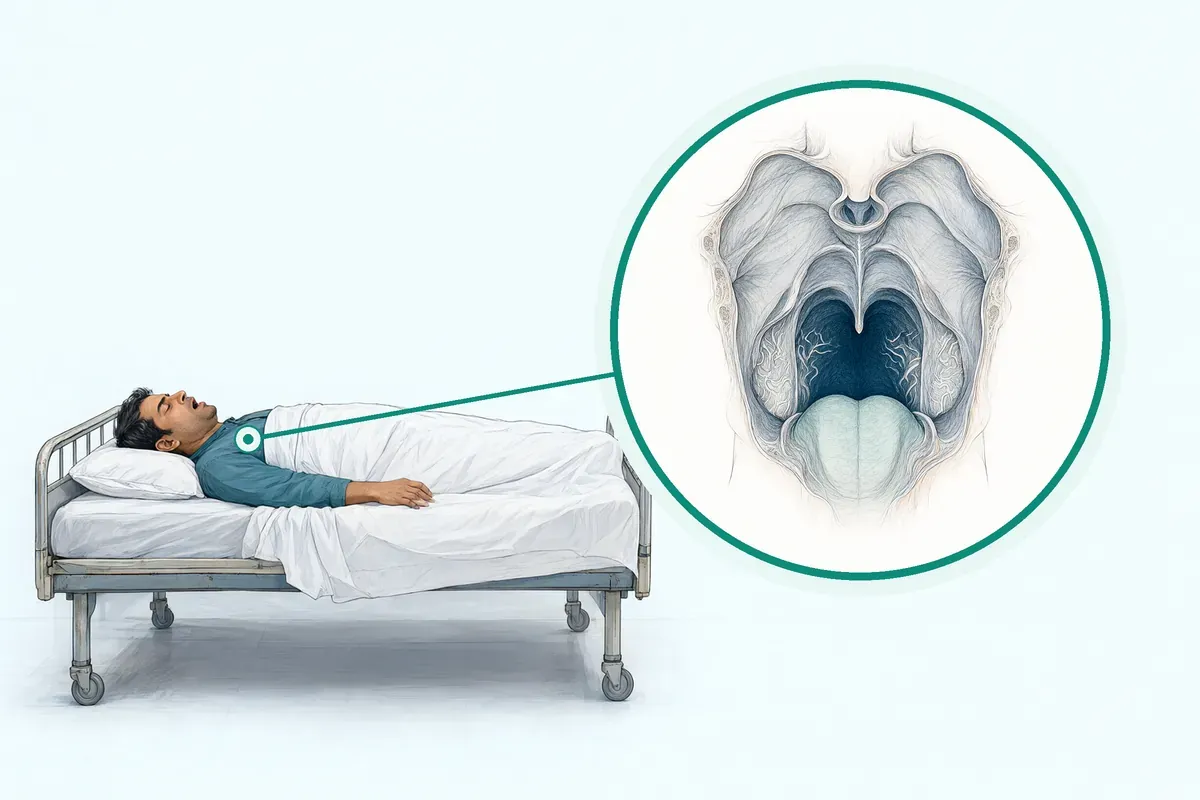
When your throat muscles relax while you sleep, tissues in your upper airway can collapse inward. This narrowing limits the flow of air into your lungs. You may awaken briefly many times each night to reopen the airway, though you might not remember waking up. Over time, these interrupted breathing cycles cause sleep fragmentation and place strain on your heart and circulation.
Snoring often happens when moving air vibrates these narrowed or floppy tissues in your throat or palate. When the airway shuts down further, airflow drops or stops entirely. At Jaipur Hospital, our surgical team evaluates the physical shape of your throat, nose, and palate to identify where these blockages take place.
Symptoms of sleep apnea and signs needing urgent care
- Chest pain or angina at night
- Shocks from implanted defibrillator
Excessive daytime sleepiness is recognised as the most prominent symptom of obstructive sleep apnea. Even after spending a full night in bed, you may feel heavy fatigue, morning sluggishness, or a constant urge to sleep during daytime tasks. Sleep disturbances are common and frequently go unnoticed or unaddressed among middle-aged and older adults.
However, only a fraction of people with an apnea-hypopnea index of five or higher report daytime sleepiness. In research studies, one investigation found no clear link between daytime sleepiness and sleep apnea in women.
Loud, persistent snoring is another common sign that breathing passages are struggling to stay open. Family members or your attendant may observe choking sounds, gasping, or pauses in your breathing through the night.
In published studies, obstructive sleep apnea with excessive daytime sleepiness was noted in 6 percent of men (with a range of 3 to 18 percent) and in 4 percent of women (with a range of 1 to 17 percent).
Certain warning signs require urgent medical care the same day. You must seek immediate attention at an emergency department if you notice:
- Severe nocturnal drops in oxygen levels or sudden gasping with blue lips
- Irregular heart rhythms or sudden racing heartbeats during sleep
- Chest pain or angina occurring in the middle of the night
- Signs of right-sided heart strain or waking with severe shortness of breath
- Appropriate shocks delivered from an implanted cardioverter-defibrillator
Causes of airway blockage and who is at higher risk
- Excess weight
- Fatty tissue around the neck crowds the throat
- Medical conditions
- High blood pressure, heart failure, stroke, diabetes linked to OSA
- Physical features
- Enlarged uvula, large tonsils, low soft palate, jaw abnormalities
Obstructive sleep apnea is more common in men than in women, and the likelihood of developing it rises with age and excess weight. Across eleven epidemiological studies published between 1993 and 2013, the average prevalence of obstructive sleep apnea with an index of five or more events per hour was 22 percent in men and 17 percent in women.
In studies from 2008 and 2013, it was reported in 37 percent of men and 50 percent of women. Overall, recorded rates of this condition in community studies have risen over time. Approximately 34 percent of middle-aged men and 17 percent of middle-aged women meet diagnostic criteria for the condition.
Excess body weight predisposes people to airway narrowing. Extra fatty tissue around the neck and soft palate can crowd the throat and press down on breathing passages during sleep. In people with metabolic syndrome, studies show the prevalence of moderate to severe obstructive sleep apnea is around 60 percent. Obesity is expanding globally, and the prevalence of sleep apnea is rising alongside it.
Other medical conditions also share strong links with airway blockages. The condition appears in 40 to 80 percent of patients who have high blood pressure, heart failure, coronary artery disease, pulmonary hypertension, irregular heart rhythms like atrial fibrillation, or a previous stroke. Cross-sectional studies also demonstrate an association between sleep apnea and diabetes mellitus.
Smoking and alcohol consumption have been suggested as risk factors as well, though medical study findings on these habits remain conflicting. Physical features, such as an enlarged uvula, large tonsils, a low soft palate, or jaw abnormalities, also increase the chance of physical obstruction.
How obstructive sleep apnea is diagnosed: examination and tests
- OPD evaluation of symptoms and airway
- Polysomnography or home sleep test
- Laboratory study if home test unclear
- Drug-induced sleep endoscopy for surgery planning
A medical assessment begins with an evaluation of your symptoms, sleep patterns, and airway anatomy in the OPD. Polysomnography, commonly known as a formal sleep study, is the standard diagnostic test for confirming obstructive sleep apnea in adults when clinical concerns arise.
Medical guidelines recommend polysomnography, or home sleep apnea testing with an adequate device, for uncomplicated adults who show signs of moderate to severe disease. If an initial home sleep test returns negative, inconclusive, or technically inadequate, a full laboratory sleep study is recommended.
In some situations, home testing is not advised.
Guidelines recommend laboratory polysomnography instead of home testing for patients with:
- Significant heart or lung disease
- Weakness in breathing muscles from nerve conditions
- Suspected sleep hypoventilation
- Chronic opioid medicine use
- Severe insomnia
- A history of stroke
A split-night diagnostic protocol during a sleep study may be suggested by your physician when clinically appropriate. If your first sleep test appears normal but your doctor still strongly suspects sleep apnea, a second sleep study may be considered.
Screening for sleep apnea is also recommended for patients dealing with hard-to-control high blood pressure, pulmonary hypertension, or atrial fibrillation that returns after medical procedures. In cardiovascular medical practice, sleep apnea is frequently underrecognised and undertreated. Formal sleep testing is also reasonable for patients with class II to IV heart failure who experience daytime sleepiness or suspected sleep-disordered breathing.
When surgery is being considered, our surgical team evaluates the exact internal areas where collapse occurs. Patients may undergo a drug-induced sleep endoscopy. This procedure replicates natural sleep inside the operating room using an infusion of a calming medicine called propofol.
Your surgeon examines the airway with a thin camera to observe whether the palate collapses from front to back or in a circular, concentric shape.
Treatment options without surgery and when sleep surgery is advised
All patients diagnosed with obstructive sleep apnea should be considered for treatment, which includes lifestyle adjustments and weight management where appropriate. Regular exercise and weight loss serve as effective steps for managing obstructive sleep apnea. For patients with severe morbid obesity, bariatric surgery plays a recognised role in managing sleep apnea. Currently, there are no effective pharmacological medicines available from a chemist to resolve sleep apnea.
Continuous positive airway pressure, known as CPAP, is a standard non-surgical therapy. It delivers pressurised air through a mask to keep your airway open while you sleep. In clinical studies, CPAP significantly reduced snoring and daytime sleepiness, and it improved mood and sleep-related quality of life.
In one trial, three months of continuous positive airway pressure treatment significantly reduced blood pressure, blood triglyceride levels, and visceral fat. For people with mild to moderate disease, or for those who cannot tolerate CPAP masks, oral dental appliances can be considered. Follow-up sleep testing is recommended to assess how well non-surgical treatments are working.
Sleep apnea surgery is typically recommended when non-surgical treatments like CPAP or oral appliances fail to relieve symptoms, or when physical obstructions are significant. In medical practice, 40 to 60 percent of patients struggle to use or tolerate CPAP therapy.
Surgery is also considered for severe anatomical upper airway blockages, craniofacial or jaw abnormalities, multilevel airway collapse identified on sleep endoscopy, or persistent sleep apnea in patients with severe obesity.
Surgical procedures modify the soft tissues of the throat or facial skeleton to enlarge the airway.
Common options include:
- Uvulopalatopharyngoplasty to remove excess tissue from the soft palate and tonsils
- Radiofrequency tissue reduction
- Nasal procedures such as septoplasty or turbinate reduction to improve airflow and aid breathing
- Hypoglossal nerve stimulation implants that move the tongue forward during sleep
Your surgeon will advise which option suits your specific airway anatomy.
Preparing for snoring and sleep surgery
When you plan for snoring and sleep surgery at Jaipur Hospital, your care begins with a thorough evaluation in our OPD. Polysomnography is the standard diagnostic test for obstructive sleep apnea before any surgery is planned.
In some cases, a home sleep apnea test is used, but a full sleep study in a laboratory is needed if you have significant heart disease, lung conditions, muscle weakness, or a history of stroke. If a home sleep test is unclear, a laboratory sleep study is recommended.
For patients considering nerve stimulation, your surgeon will arrange a drug-induced sleep endoscopy. This short test uses an infusion of propofol to recreate natural sleep. It allows our surgical team to look directly at whether the palate collapses from front to back or in a circular pattern.
Before the day of your operation, you will attend a pre-anaesthesia check. You will need routine blood tests, an ECG, and a chest X-ray at our in-house diagnostic laboratory and imaging facility. Tell your doctor about all medicines, vitamins, and herbal supplements you take at home.
Discuss any blood-thinning tablets or diabetes medicines with your doctor, who will tell you how to take them safely before surgery. Never stop or change any regular prescription on your own.
Fasting is necessary before general anaesthesia to keep your airway clear and safe during surgery. You will typically be instructed not to eat any solid food or drink liquids for at least six to eight hours before your admission time. Our staff will tell you the exact time to begin fasting based on your scheduled theatre slot.
On the day of admission, bring your previous sleep study reports, all medical records, government identification cards, and your insurance or scheme documents. Bring your current medicines in their original packaging so our team can review them. You may also bring loose, comfortable clothing and personal toiletries for your stay. You will need one adult attendant to stay with you in the hospital room during your admission.
How snoring and sleep surgery is done
- UPPP
- Removes excess tissue from soft palate, uvula, tonsils
- Radiofrequency ablation
- Stiffens tissue and reduces volume at palate or tongue base
- Nasal correction
- Septoplasty, turbinate reduction, or valve repair
- Hypoglossal nerve stimulation
- Implant activates nerve to move tongue forward during sleep
On the day of your procedure, you will be admitted to Jaipur Hospital and prepared in the pre-operative area. A member of our nursing team will verify your details, check your vital signs, and place an intravenous line. Sleep surgery is performed under general anaesthesia in our modular operation theatres, so you remain asleep throughout the procedure. The operation time is typically 1 to 3 hours.
Surgical modification of the soft tissues of the throat or the facial skeleton works by enlarging the upper airway. There are several surgical options, and your surgeon will advise which procedure suits your specific airway anatomy:
- Uvulopalatopharyngoplasty (UPPP): This technique involves removing excess tissue from the soft palate, uvula, and sometimes the tonsils to widen the airway and prevent collapse during sleep. It treats obstruction behind the palate.
- Radiofrequency ablation of the palate or tongue base: This option uses targeted energy to stiffen tissue and reduce excess volume at the soft palate or tongue base, helping to prevent tissue collapse during sleep.
- Nasal obstruction correction: Procedures such as septoplasty, turbinate reduction, or valve repair correct structural blockages inside the nose. This improves airflow and can assist patients who struggle to use nasal CPAP masks.
- Hypoglossal nerve stimulation: This approach uses an implantable neurostimulator to activate the hypoglossal nerve during sleep. It is an option for select patients with moderate-to-severe obstructive sleep apnea who have difficulty using CPAP therapy. The procedure approaches three areas: an electrode cuff is placed around the specific nerve fibres that move the tongue forward, a pulse generator is placed over the chest muscle, and a breathing sensor lead is placed between the ribs.
After the operation is completed, the anaesthesia team will reverse your medications. You will then be moved to the recovery area and monitored closely before transferring to your hospital room.
Risks and possible complications of sleep surgery
Every surgical procedure carries potential risks. As with any surgery under general anaesthesia, there are risks of bleeding, local infection, temporary breathing difficulties, and reactions to anaesthetic medicines. Your surgical team takes careful precautions before, during, and after the operation to reduce these risks.
Throat and palate operations commonly cause significant throat pain, difficulty swallowing, temporary changes in voice, or a sensation of fluid entering the back of the nose during drinking. These symptoms usually improve as tissues heal over several weeks. When surgical work involves the nose, patients may experience temporary nasal congestion, crusting, and minor bleeding from the nostrils.
Procedures involving the base of the tongue carry a risk of temporary tongue swelling, numbness, or altered movement. For hypoglossal nerve stimulation implants, specific surgical risks include lead movement, temporary tongue weakness, device malfunction, or infection around the chest or neck incisions.
In studies, the pattern of airway collapse influences the outcome; concentric collapse of the palate was associated with decreased success, which is why patients with that pattern are not selected for the implant.
Studies show that non-surgical options like CPAP can effectively reduce snoring and daytime sleepiness. However, between 40% and 60% of patients fail or cannot tolerate CPAP therapy in clinical practice. Sleep apnea itself is associated with considerable health risks, including high blood pressure, stroke, and coronary artery disease.
Your surgeon will review all potential complications with you during your OPD consultation so you can make an informed choice.
Recovery and aftercare for sleep surgery
- Hospital stay 1 to 2 nights for monitoring
- Hypoglossal nerve stimulator recovery 4 to 6 weeks for incisions to heal
- Follow-up sleep study After activation to fine-tune settings
After sleep surgery, you will typically stay in the hospital for 1 to 2 nights so our team can monitor your breathing and manage any discomfort. During the first few days, throat pain and swelling are common, especially after palate or tonsil surgery.
You will be started on clear liquids and smooth, cool foods such as:
- Porridge
- Curd
- Strained soups
Avoid hot, spicy, rough, or acidic foods that can irritate the surgical site.
Most patients need 2 to 3 weeks of recovery time at home before resuming normal work and daily routines. If you receive a hypoglossal nerve stimulator, full recovery of the surgical incisions typically takes 4 to 6 weeks. Rest quietly at home and avoid strenuous exercise, heavy lifting, and bending forward during this healing phase.
Take all medicines prescribed by your surgeon exactly as directed, and collect them from the in-house pharmacy or your local chemist. If you receive an implantable neurostimulator, the device is not turned on immediately after surgery. In clinical protocols, the device is activated by sleep medicine doctors about one month after implantation.
Over the following month, the stimulation strength is gradually increased as you adapt to it. You will then undergo an overnight sleep study to adjust and fine-tune the settings.
Follow-up sleep testing should be performed after surgery to assess how effectively the airway has opened. Attend all scheduled OPD visits so your surgeon can inspect the healing tissue.
Call Jaipur Hospital or come to our 24x7 emergency department immediately if you notice active bleeding from the mouth or nose, sudden difficulty breathing, high fever, inability to swallow liquids, or spreading redness around any surgical cut. Your attendant should have our emergency contact details ready during your recovery period.
Results and long-term outcomes in studies
- 29.3 events per hour Baseline AHI in stimulation study
- 46 events per hour Preoperative AHI in 2017 group
- 4.6 events per hour Postoperative AHI in 2017 group
The outcome of snoring and sleep surgery depends on your individual airway anatomy, body weight, and the surgical technique used. Clinical trials evaluate sleep surgery by measuring changes in the apnea-hypopnea index (AHI), which counts how many times your breathing pauses per hour of sleep.
Uvulopalatopharyngoplasty (UPPP) has served as a primary surgical procedure for obstructive sleep apnea for decades. However, a lack of enduring outcomes over the long term has been an observed concern with UPPP in medical literature.
Studies examining upper-airway stimulation have shown significant improvements in both objective sleep measurements and subjective symptom scores.
In one study evaluating 126 participants, 83% of whom were men with a mean age of 54.5 years and a mean body mass index of 28.4, the median AHI score decreased 68% at 12 months, dropping from 29.3 events per hour at baseline to 9.0 events per hour.
In another published group of 27 patients treated in 2017, the average preoperative AHI dropped from 46 down to 4.6 events per hour. A published five-year follow-up study showed that these improvements remained enduring over time.
Weight loss and regular exercise remain effective non-surgical treatments that support long-term breathing stability. Because body weight and age can change over time, sleep apnea symptoms can sometimes return. Ongoing follow-up with your sleep care team ensures that any recurring breathing pauses are identified and managed promptly.
Cost of snoring and sleep surgery and insurance in Jaipur
At Jaipur Hospital, the cost of snoring and sleep surgery depends on the exact procedure required to open your airway. For soft palate and nasal procedures, the price is typically ₹80,000 to ₹2,50,000. For hypoglossal nerve stimulation surgery, the price is typically ₹10,00,000 to ₹18,00,000. This is the typical price range in India. You may ask our team for a personalised estimate based on your specific clinical needs.
Several factors change the final cost of care.
These include:
- Choice of surgical technique
- Whether multiple airway levels are operated on during the same session
- Duration of theatre time
- Type of hospital room selected
- Total length of your hospital stay
Pre-operative sleep studies, diagnostic endoscopy, and medications from the chemist also influence overall expenses.
Jaipur Hospital is a NABH-accredited multispeciality hospital that works with government healthcare schemes and private insurance providers. We accept Rajasthan Government Health Scheme (RGHS), MAA Yojana, Central Government Health Scheme (CGHS), and a panel of private insurers and Third Party Administrators (TPAs).
If you plan to use government schemes or cashless private mediclaim, visit our hospital desk with your scheme card, policy documents, and doctor referral before your planned admission date. Our staff will assist you with the necessary pre-authorisation paperwork.